
BIOL-330 · Lesson 12 of 12 · 31 min
Capstone: public health microbiology, outbreaks and biosafety
Public health microbiology turns the science of the previous eleven lessons into protection for whole populations. Its laboratories identify pathogens and their resistance, link cases that share a source, detect outbreaks early and supply the evidence for recalls, advisories and control measures. Its biosafety rules let people work with dangerous organisms without infecting themselves or the public. This capstone describes how surveillance and outbreak investigation work, applies the methods to an invented outbreak with real analytical tools, and sets out how biosafety and biosecurity are governed in Canada and the United States. Epidemiological modelling and workplace infection prevention were covered in HSE-245, and clinical diagnosis and treatment belong to health and medicine courses; the emphasis here is on what the microbiology laboratory contributes.
Surveillance: seeing the signal
Public health surveillance is the ongoing, systematic collection, analysis and interpretation of health data to guide action. For infectious diseases, the foundation is the list of notifiable diseases that clinicians and laboratories must report to public health authorities, such as salmonellosis, listeriosis, Shiga toxin-producing E. coli infection, tuberculosis, measles and invasive meningococcal disease. Reports from local health units flow to provincial, territorial or state authorities and then to national agencies. Surveillance is always incomplete, because many people with mild illness never see a doctor, few of those who do are tested, and not every positive test is reported. For every laboratory-confirmed case of salmonellosis, burden studies estimate that dozens of illnesses occur in the community, a ratio described as the surveillance pyramid.
Laboratory-based surveillance adds the detail that makes outbreak detection possible. Public health laboratories receive isolates or specimens from hospital and community laboratories and characterize them further: serotyping, antimicrobial susceptibility testing and, increasingly, whole-genome sequencing (WGS). Comparing isolates across a whole country reveals clusters that no single clinic would notice, such as a handful of cases with indistinguishable Salmonella genomes scattered across several provinces or states. Before WGS, the standard method was pulsed-field gel electrophoresis, which compared DNA fragment patterns. Since the late 2010s the PulseNet networks in Canada and the United States have replaced it with WGS, which gives far finer resolution and also reveals resistance and virulence genes.
In Canada, the Public Health Agency of Canada’s National Microbiology Laboratory (NML) in Winnipeg is the national reference laboratory and coordinates PulseNet Canada with provincial public health laboratories. It also hosts Canada’s only containment level 4 laboratory for human pathogens, sharing its building, the Canadian Science Centre for Human and Animal Health, with the Canadian Food Inspection Agency’s National Centre for Foreign Animal Disease. The Canadian Notifiable Disease Surveillance System compiles national case data, and PHAC coordinates multi-jurisdictional outbreak investigations through its Outbreak Investigation Coordinating Committee, working with provinces, territories, CFIA and Health Canada. For comparison, the US CDC in Atlanta runs PulseNet USA and the National Notifiable Diseases Surveillance System.
Reading genomes for outbreaks
WGS-based outbreak detection compares isolates by the number of single-nucleotide polymorphisms (SNPs) between their genomes, or by the number of allele differences across a standard set of genes in core-genome multilocus sequence typing (cgMLST). Isolates from a single recent source are expected to differ by only a few SNPs, because there has been little time for mutations to accumulate. Laboratories use organism-specific thresholds as a guide, often about 0 to 10 SNPs or alleles for Salmonella and Listeria clusters, but no threshold is absolute: some long-running outbreaks, such as Listeria persisting in a plant for years, accumulate more diversity, and some unrelated isolates from a highly clonal lineage differ by very few SNPs. Genomic links are therefore always combined with epidemiological and traceback evidence. Genomes are also shared internationally through databases such as the NCBI Pathogen Detection system, which in 2024 held well over a million bacterial genomes, so that a cluster in one country can be matched to isolates from food or patients elsewhere.
import numpy as np

# Invented SNP distance matrix for 9 Salmonella Enteritidis isolates (core-genome SNPs)
ids = ["P01", "P02", "P03", "P04", "P05", "P06", "F01", "S01", "S02"]
D = np.array([
 [ 0,  1,  2,  0,  1,  3,  1, 48, 52],
 [ 1,  0,  1,  1,  2,  2,  0, 47, 51],
 [ 2,  1,  0,  2,  3,  3,  1, 49, 50],
 [ 0,  1,  2,  0,  1,  3,  1, 48, 52],
 [ 1,  2,  3,  1,  0,  4,  2, 49, 53],
 [ 3,  2,  3,  3,  4,  0,  2, 50, 54],
 [ 1,  0,  1,  1,  2,  2,  0, 47, 51],
 [48, 47, 49, 48, 49, 50, 47,  0, 12],
 [52, 51, 50, 52, 53, 54, 51, 12,  0]])
threshold = 5
# single-linkage clustering: isolates joined if any chain of links <= threshold
n = len(ids); parent = list(range(n))
def find(i):
    while parent[i] != i:
        parent[i] = parent[parent[i]]; i = parent[i]
    return i
for i in range(n):
    for j in range(i + 1, n):
        if D[i, j] <= threshold:
            parent[find(i)] = find(j)
clusters = {}
for i in range(n):
    clusters.setdefault(find(i), []).append(ids[i])
for k, members in enumerate(clusters.values(), 1):
    idx = [ids.index(m) for m in members]
    sub = D[np.ix_(idx, idx)]
print(f"cluster {k}: {members} max pairwise SNPs = {sub.max()}")cluster 1: ['P01', 'P02', 'P03', 'P04', 'P05', 'P06', 'F01'] max pairwise SNPs = 4 cluster 2: ['S01'] max pairwise SNPs = 0 cluster 3: ['S02'] max pairwise SNPs = 0
In the invented data, six patient isolates and one food isolate fall within a few SNPs of each other, while two sporadic isolates differ from them by about fifty SNPs and from each other by twelve. The genomic evidence supports a common source for the cluster and links it to the food sample, but it cannot say by itself how the food became contaminated or whether other foods were involved.
Investigating an outbreak
Outbreak investigations follow a well-established sequence of steps, although in practice several happen at once. Investigators verify the diagnosis and confirm that an outbreak exists, meaning more cases than expected for the place and time; write a case definition with clinical, laboratory, time, place and person criteria, often in tiers of confirmed, probable and possible; find cases systematically; describe them by time, place and person; form hypotheses about the source and mode of transmission; test the hypotheses with analytical studies; implement control measures as soon as there is enough evidence, without waiting for certainty; and communicate findings. The laboratory contributes at almost every step, from confirming the pathogen to linking cases genomically and testing suspected foods, water or environmental samples.
The epidemic curve, a histogram of cases by date of illness onset, is the first picture of any outbreak. A sharp peak whose width is about one incubation period suggests a point source, such as a single meal. A curve with several peaks or a long plateau suggests a continuing common source, such as a contaminated product on sale for weeks, and successive waves one incubation period apart suggest person-to-person propagation. If the pathogen and its incubation period are known, the likely exposure date can be estimated by counting back from the peak by the median incubation period.
An invented outbreak: the Riverbend community supper
The following scenario, with invented data, shows how these steps fit together. On a Monday, a regional public health unit receives laboratory reports of Salmonella Enteritidis from five adults who live in the small town of Riverbend. Interviews reveal that all five attended a community fundraising supper on the previous Saturday evening, at which about 120 people ate. Investigators decide to treat the supper attendees as a cohort.
Case definition: a person who attended the Riverbend supper and developed diarrhoea (three or more loose stools in 24 hours) or fever with abdominal cramps between the supper and the following Thursday; confirmed cases also have a stool culture positive for S. Enteritidis with the outbreak genome. Using the supper’s sign-up list, investigators reach 104 attendees by telephone with a standard questionnaire about symptoms, onset times and the foods eaten, and identify 38 cases, 14 of them laboratory confirmed.
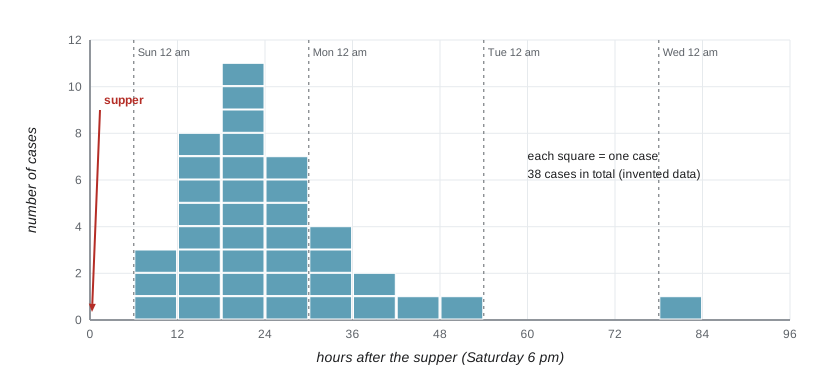
The epidemic curve shows a single peak about 18 to 24 hours after the supper, with all but one case within three days. That shape and timing fit a point-source exposure at the supper and the usual incubation period of non-typhoidal Salmonella, about 6 hours to 3 days. The late case could be a secondary infection in a household or an unusually long incubation, and is examined separately.
To identify the vehicle, investigators compare attack rates, the proportion of people who became ill, between those who ate and those who did not eat each food. The relative risk is the ratio of the two attack rates; a value well above 1, with a confidence interval excluding 1, points to the food.
import numpy as np
from scipy.stats import fisher_exact

# Invented cohort data: (ill & ate, well & ate, ill & not eaten, well & not eaten)
foods = {
    "roast turkey":           (30, 40,  8, 26),
    "mashed potatoes":        (34, 54,  4, 12),
    "coleslaw":               (17, 30, 21, 36),
    "homemade mayonnaise dip":(35, 12,  3, 54),
    "apple pie":              (20, 35, 18, 31),
}
print(f"{'food':26s} {'AR eaten':>9s} {'AR not':>8s} {'RR':>6s}  {'95% CI':>13s}  {'Fisher p':>9s}")
for food, (a, b, c, d) in foods.items():
    ar1, ar0 = a / (a + b), c / (c + d)
    rr = ar1 / ar0
    se = np.sqrt(1/a - 1/(a + b) + 1/c - 1/(c + d))          # SE of ln(RR)
    lo, hi = np.exp(np.log(rr) - 1.96 * se), np.exp(np.log(rr) + 1.96 * se)
    p = fisher_exact([[a, b], [c, d]])[1]
    print(f"{food:26s} {ar1:9.0%} {ar0:8.0%} {rr:6.2f}  ({lo:5.2f}, {hi:5.2f})  {p:9.2g}")
print("cases who did not eat the dip:", foods["homemade mayonnaise dip"][2])food AR eaten AR not RR 95% CI Fisher p roast turkey 43% 24% 1.82 ( 0.94, 3.54) 0.082 mashed potatoes 39% 25% 1.55 ( 0.64, 3.76) 0.4 coleslaw 36% 37% 0.98 ( 0.59, 1.63) 1 homemade mayonnaise dip 74% 5% 14.15 ( 4.64, 43.11) 6.1e-14 apple pie 36% 37% 0.99 ( 0.60, 1.64) 1 cases who did not eat the dip: 3
The homemade mayonnaise dip stands out: three-quarters of those who ate it became ill, compared with about one in twenty of those who did not, a relative risk of about 14 with a confidence interval far from 1, and it accounts for 35 of the 38 cases. Turkey shows a modest association, which is expected because most people who ate the dip also ate turkey; a stratified or multivariable analysis would test whether turkey has any effect independent of the dip. Three cases who did not report eating the dip could reflect recall error, cross-contamination of other foods on the buffet or secondary spread.
The laboratory evidence completes the picture. Leftover dip from a volunteer’s refrigerator yields S. Enteritidis with a genome within one SNP of the patient isolates (the F01 isolate in the clustering above). The dip was made with raw shell eggs from a small local flock and held at room temperature for several hours before serving. S. Enteritidis can infect the reproductive tissues of laying hens and contaminate the inside of intact eggs, which is why food safety guidance in both countries recommends pasteurized eggs for dishes that will not be cooked. Investigators trace the eggs to the farm, where environmental samples from the henhouse also yield the outbreak strain, and the agriculture authority works with the farm on flock testing and control.
Control measures follow at each stage, before the investigation is complete: advice to attendees on hygiene and when to seek care, exclusion of ill food handlers from work, removal of the remaining dip and eggs, and a public advisory if eggs from the flock had been sold more widely. The final report records the investigation and its lessons, such as training for volunteer cooks at community events, so that the next outbreak can be prevented rather than investigated.
Biosafety: protecting workers and the public
Laboratories that handle pathogens are designed and operated so that the people working in them, and the community outside, are not exposed. Biosafety is built on risk assessment. Pathogens are assigned to risk groups according to how severe the disease they cause is, how easily they spread, and whether effective treatment and prevention exist; activities are then carried out at a containment or biosafety level matched to the risk of the organism and the procedure.
| Risk group | Individual and community risk | Examples | Typical containment |
|---|---|---|---|
| 1 | Low individual and community risk; unlikely to cause disease in healthy adults | E. coli K-12, Bacillus subtilis, Saccharomyces cerevisiae | Level 1: basic laboratory practices |
| 2 | Moderate individual risk, low community risk; disease rarely serious and treatment or prevention available | Salmonella, Staphylococcus aureus, hepatitis B virus, influenza (seasonal) | Level 2: restricted access, biological safety cabinets for aerosol-producing work, personal protective equipment |
| 3 | High individual risk, low community risk; serious disease, usually treatable or preventable, may spread by aerosol | Mycobacterium tuberculosis, SARS-CoV-2 (for culture work), West Nile virus | Level 3: controlled airflow, sealed rooms, respiratory protection, all work in safety cabinets |
| 4 | High individual and community risk; serious disease, readily transmitted, often without effective treatment | Ebola, Marburg and Nipah viruses | Level 4: positive-pressure suits or cabinet lines, dedicated buildings and air handling |
Containment rests on three layers. Good microbiological practice and training are the most important: most laboratory-acquired infections result from human error, such as needle-stick injuries, splashes and aerosols from routine procedures. Safety equipment, especially Class II biological safety cabinets that draw air away from the worker through HEPA filters, provides primary containment around the work. Facility design, from hand-washing sinks at level 2 to directional airflow, sealed surfaces, effluent decontamination and redundant HEPA-filtered exhaust at higher levels, provides secondary containment. Lesson 4’s decontamination methods, autoclaving and validated chemical disinfection, apply to all waste leaving a containment laboratory. Biosafety also overlaps with biosecurity, the protection of dangerous pathogens and toxins, along with the information about them, against loss, theft or deliberate misuse, through inventories, access controls and personnel screening.
In Canada, work with human pathogens and toxins is regulated by PHAC under the Human Pathogens and Toxins Act (2009) and the Human Pathogens and Toxins Regulations (2015). Facilities working with risk group 2 or higher pathogens, or with regulated toxins, need a PHAC licence, must appoint a biological safety officer and must report laboratory exposures and other incidents. Terrestrial animal pathogens are regulated by CFIA under the Health of Animals Act. The Canadian Biosafety Standard (third edition, 2022) sets out the physical containment, operational practice and performance requirements for each containment level, and the Canadian Biosafety Handbook gives guidance on meeting them. Particular pathogens and toxins with the highest misuse potential are designated security sensitive biological agents (SSBAs), and people working with them need a Human Pathogens and Toxins Act security clearance. For comparison, the United States relies on the BMBL guidance manual (sixth edition, 2020) and on the Federal Select Agent Program for the most dangerous agents and toxins.
Some legitimate research could produce knowledge, methods or organisms that might be misused, such as work that would make a pathogen more transmissible or more resistant to countermeasures. This is called dual-use research of concern, and both countries review such research before it is funded or carried out. Policies have been changing rapidly; for example, the United States issued a new federal policy on dual-use research and enhanced pandemic pathogens in 2024 and in 2025 ordered a pause on certain gain-of-function research pending a replacement policy. Researchers must check the current requirements of their institutions, funders and national regulators before planning such work (status reviewed October 2026). Governance of this kind is a matter of institutional review, risk assessment and transparency; it is not something individual researchers decide alone.
Putting the course together
The Riverbend investigation drew on almost every lesson. Lesson 1’s culture and identification methods isolated the organism; lesson 3’s counting methods and lesson 4’s growth limits explain why a dip held at room temperature became dangerous; lesson 5’s susceptibility testing would guide any treatment and surveillance of resistance; lesson 7’s genomics linked patients, food and farm; lesson 10’s caution about correlation applies to food histories as much as to microbiomes; and lesson 11’s food safety controls show what should have prevented the outbreak. Microbiology is a single, connected science, and public health is one of the places where that connection matters most.
Worked problem
Estimating the exposure time from an epidemic curve
In another invented outbreak, onset times of 22 norovirus cases cluster with a median at 10 am on a Wednesday, and the range runs from 6 pm on Tuesday to 11 pm on Wednesday. Norovirus has a median incubation period of about 33 hours (range roughly 12 to 48 hours). When did exposure most likely occur?
Show solution
- Count back one median incubation period from the median onset: 10 am Wednesday minus 33 hours is about 1 am Tuesday.
- Check with the range: exposure must precede the earliest case (6 pm Tuesday) by at least the minimum incubation (12 hours), so it happened no later than about 6 am Tuesday; and it must precede the latest case (11 pm Wednesday) by no more than the maximum (48 hours), so it happened no earlier than about 11 pm Monday.
- The estimates converge on late Monday night to Tuesday morning, so investigators should focus on meals and events during that window, such as a Tuesday breakfast or a late Monday function.
Answer: Most likely late Monday night or early Tuesday. Counting back from the curve narrows the exposure window before any interviews or laboratory results are available.
Common mistakes
MistakeWaiting for laboratory confirmation before taking any control measures.
InsteadAct as soon as the evidence is sufficient to protect people; confirmation can follow.
MistakeTreating a SNP threshold as proof that isolates share a source.
InsteadGenomic closeness supports a link but must be combined with epidemiological and traceback evidence.
MistakeComparing attack rates without considering foods eaten together.
InsteadCorrelated exposures produce secondary associations; stratified or multivariable analysis separates them.
MistakeAssuming surveillance counts equal the number of people infected.
InsteadMost infections are never tested or reported; the surveillance pyramid scales confirmed cases up to community burden.
MistakeEquating containment level with the hazard of the organism alone.
InsteadContainment depends on the organism and the procedure; culturing large volumes may need more containment than diagnostic testing.
MistakeThinking biosafety is mainly about facility design.
InsteadTraining and good practice prevent most exposures; equipment and design provide additional layers.
Summary and key terms
- Surveillance of notifiable diseases is incomplete but systematic; laboratory surveillance with whole-genome sequencing detects dispersed clusters.
- SNP or cgMLST distances link isolates; thresholds guide but do not prove a common source.
- Outbreak investigation verifies the outbreak, defines cases, describes time, place and person, tests hypotheses and acts early.
- Epidemic curves reveal point-source, continuing-source and propagated outbreaks and allow exposure times to be estimated.
- Attack rates and relative risks with confidence intervals identify vehicles in cohort studies; laboratory and traceback evidence confirm them.
- Risk groups 1 to 4 and matching containment levels, good practice, safety cabinets and facility design protect workers and the public.
- Canada regulates pathogen work under the Human Pathogens and Toxins Act and the Canadian Biosafety Standard; the United States uses the BMBL and the Federal Select Agent Program.
- notifiable disease
- A disease that clinicians and laboratories are legally required to report to public health authorities.
- whole-genome sequencing
- Determining the complete genome of an isolate, used to compare isolates at high resolution.
- case definition
- Standard criteria for deciding whether a person is counted as a case in an investigation.
- epidemic curve
- A histogram of cases by date or time of illness onset.
- point-source outbreak
- An outbreak in which people are exposed to the same source over a brief period.
- attack rate
- The proportion of an exposed group who become ill.
- relative risk
- The ratio of the attack rate in the exposed to that in the unexposed.
- risk group
- A classification of pathogens by the hazard they pose to individuals and the community.
- biological safety cabinet
- A ventilated enclosure that uses HEPA-filtered airflow to protect workers, samples and the environment.
- dual-use research of concern
- Legitimate research that could be misapplied to cause significant harm and therefore requires special oversight.
Practice problems
Work each problem on paper first, then reveal the answer to check.
What is the surveillance pyramid?
Show answer
The idea that reported laboratory-confirmed cases are a small fraction of all infections in the community.
Why did WGS replace pulsed-field gel electrophoresis in PulseNet?
Show answer
It gives much higher resolution and also reveals resistance and virulence genes.
What three elements of time, place and person might a case definition include?
Show answer
Onset within a date range, attendance at an event or residence in an area, and characteristics such as age or symptoms.
What epidemic curve shape suggests person-to-person spread?
Show answer
Successive waves about one incubation period apart.
Among 50 people who ate a salad, 20 became ill; among 50 who did not, 5 became ill. What is the relative risk?
Show answer
0.40/0.10 = 4.
Why might a food eaten by most cases still not be the vehicle?
Show answer
If almost everyone ate it, including the well, its attack rate may be similar in both groups; or it was eaten with the true vehicle.
Why is mayonnaise made with raw shell eggs a hazard?
Show answer
Salmonella Enteritidis can be inside intact eggs, and the raw dip is not cooked.
Which risk group would Mycobacterium tuberculosis normally fall into?
Show answer
Risk group 3.
What does a Class II biological safety cabinet protect?
Show answer
The worker, the sample and the environment, using HEPA-filtered airflow.
Name the Canadian and US documents that set biosafety requirements or guidance.
Show answer
The Canadian Biosafety Standard (with the Canadian Biosafety Handbook) and the BMBL.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.