
LES-203 · Lesson 7 of 12 · 23 min
Breath, blood and drug evaluation evidence
▶ Video coming soon A video version of this lesson is on the way.
At the Port Ardent station, Officer Femi Okoro, who holds an Ohio Department of Health operator permit for the station's Intoxilyzer 8000, began a twenty-minute observation period at 23:44, watching to make sure Lindqvist did not burp, vomit or put anything in his mouth. The instrument ran its own checks, and Lindqvist provided two breath samples at 00:05 and 00:08 as the instrument's test sequence requires. The results were 0.118 and 0.112 grams per 210 liters of breath, and the lower result, 0.112, is the one used as the test result. Okoro printed the ticket, and Ruiz completed the administrative license suspension form and served it on Lindqvist.
This lesson covers the evidence that proves a driver's concentration of alcohol or drugs: evidential breath tests, blood samples and drug recognition evaluations. Kowalczyk calls it 'the part of the file where science meets the rules of evidence.' The science is reliable when the instrument is approved, maintained and operated correctly. The rules of evidence decide whether the result reaches the court at all.
How evidential breath instruments work
When a person drinks, alcohol is absorbed into the blood, mostly from the small intestine, and carried throughout the body. In the lungs, alcohol passes from the blood into the air in the tiny air sacs called alveoli, in a fairly constant ratio. Evidential breath instruments measure the alcohol in a sample of deep lung air and report the result as a blood concentration in grams per 210 liters of breath, which Ohio law treats directly as a prohibited concentration. Most modern instruments use infrared spectroscopy, which measures how much infrared light at certain wavelengths the alcohol absorbs, and some also use a fuel cell, which produces a small electric current in proportion to the alcohol present.
The observation period protects against mouth alcohol, which is alcohol in the mouth from recent drinking, a burp, regurgitation or mouthwash. Mouth alcohol can make a breath result much higher than the true blood concentration. Instruments also look for a slope in the alcohol concentration during the breath that suggests mouth alcohol, and they test room air and a known alcohol standard before or between subject samples. Two samples that agree closely give confidence that the result is reliable.
The legal rules for breath evidence
Ohio's implied consent law, section 4511.191, says that anyone who operates a vehicle in Ohio is deemed to have consented to a chemical test of blood, breath or urine if arrested for OVI. The officer must read the implied consent advice on the BMV 2255 form, which explains the consequences of refusing or failing. Under section 4511.19(D)(1)(b), the sample must be withdrawn within three hours of the alleged violation, and the analysis must follow the Ohio Department of Health's rules in the Ohio Administrative Code, including instrument certification, calibration checks, operator permits and the observation period. Defense lawyers frequently file motions to suppress breath results for any departure from those rules, and courts require substantial compliance.
Worked problem
Checking the legal conditions
Lindqvist was last operating at 23:10, and his breath samples were taken at 00:05 and 00:08. Was the sample within the three-hour window, and what result is reported?
Show solution
- The three-hour window from 23:10 ends at 02:10.
- 00:05 and 00:08 are both well within the window: 55 and 58 minutes after the violation.
- The instrument reports the lower of the two results, 0.112.
Answer: The sample was within the window; the reported result is 0.112.
Worked problem
When the first test is late
Suppose a breath test in Ohio could not be taken until three hours and ten minutes after the violation. What happens to the result?
Show solution
- The sample was outside the three-hour window in section 4511.19(D)(1)(b).
- \[\text{3 h 10 min} > \text{3 h}\]
- Ohio courts have held that a late result may still be admitted with expert testimony on the under-the-influence charge, but not to prove the per se offense by itself.
Answer: It cannot be used by itself to prove the per se offense.
Alcohol absorption and elimination
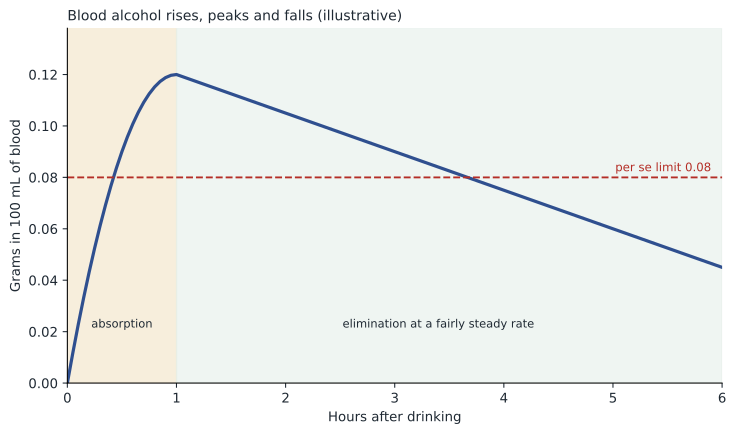
The amount of alcohol in the blood rises during the absorption phase after drinking, reaches a peak, and then falls during the elimination phase as the liver breaks alcohol down. In most people, elimination proceeds at a fairly steady rate, often taken as about 0.015 grams per 100 mL per hour, with a range of about 0.010 to 0.020. Food in the stomach slows absorption and lowers the peak. Officers are not experts in these calculations, but they should understand them, because toxicologists use them in court to estimate a driver's concentration at the time of driving, and defense lawyers raise them to argue that a driver was still absorbing alcohol and was under the limit when stopped.
Worked problem
A toxicologist's back-calculation
A toxicologist is asked to estimate a driver's blood alcohol at 22:30, when a crash happened, from a blood sample taken at 01:00 that showed 0.095. Assuming absorption was complete by 22:30 and elimination was 0.015 per hour, what was the concentration at the time of the crash? What range follows from rates of 0.010 to 0.020 per hour?
Show solution
- The time between the collision and the sample is 2.5 hours.
- \[0.095 + 2.5 \times 0.015 = 0.1325\]
- \[0.095 + 2.5 \times 0.010 = 0.120, \quad 0.095 + 2.5 \times 0.020 = 0.145\]
- Every value in the range is over the limit, which is why the estimate is useful even with uncertainty about the rate.
Answer: About 0.13, with a range of 0.120 to 0.145.
Blood samples
Blood is the most direct measure of alcohol and drug concentration and is the main sample for drugs other than alcohol. In Schmerber v. California in 1966, the U.S. Supreme Court held that a warrantless blood draw from a driver injured in a crash was reasonable because the evidence was disappearing and there was no time to get a warrant. In Missouri v. McNeely in 2013, the Court held that the natural dissipation of alcohol does not by itself create an emergency in every case; officers must get a warrant when they reasonably can. In Birchfield v. North Dakota in 2016, it held that breath tests can be required without a warrant as a search incident to arrest, but blood tests cannot, and states may not make it a crime to refuse a blood test. In Mitchell v. Wisconsin in 2019, a plurality held that when a driver is unconscious and must be taken to hospital, exigent circumstances will almost always allow a warrantless blood draw. Port Ardent officers now apply for electronic warrants for blood, which judges can sign within minutes.
| Sample | What it shows | Main limits |
|---|---|---|
| Breath | Alcohol concentration, quickly and without a needle | Only alcohol; mouth alcohol and timing rules |
| Blood | Alcohol and drug concentrations directly | Needs a warrant or valid consent unless exigent, and medical personnel |
| Oral fluid | Presence of some drugs | Screening only at the roadside; presence, not impairment |
| Urine | Presence of drugs or metabolites over a longer period | Ohio sets per se urine levels, but urine shows past use better than current impairment |
Drug recognition evaluations
Because no roadside device measures drug impairment, both countries use trained drug recognition experts, or DREs, to evaluate drivers suspected of drug impairment. The Drug Evaluation and Classification Program was developed by the Los Angeles Police Department in the 1970s and is now coordinated by the International Association of Chiefs of Police with NHTSA, and used in both countries. A DRE follows a standardized twelve-step evaluation and forms an opinion about whether the person is impaired and, if so, by which category of drug.
| Step | What the DRE does |
|---|---|
| 1. Breath alcohol test | Rules alcohol in or out as the explanation |
| 2. Interview of the arresting officer | Learns what was seen and said |
| 3. Preliminary examination and first pulse | Checks for injury or illness |
| 4. Eye examinations | HGN, vertical gaze nystagmus and lack of convergence |
| 5. Divided attention tests | Modified Romberg balance, walk-and-turn, one-leg stand, finger to nose |
| 6. Vital signs and second pulse | Blood pressure and temperature |
| 7. Dark room examinations | Pupil size in different lighting |
| 8. Muscle tone | Whether muscles are rigid or flaccid |
| 9. Check for injection sites and third pulse | Looks for signs of injected drugs |
| 10. Statements and other observations | Questions about drug use, after rights are given |
| 11. Opinion of the evaluator | Impaired or not, and which drug category or categories |
| 12. Toxicological examination | A bodily fluid sample to confirm the drug |
The DRE's opinion names one or more of seven drug categories: central nervous system depressants, central nervous system stimulants, hallucinogens, dissociative anesthetics, narcotic analgesics, inhalants and cannabis. Each category produces a typical pattern of signs. For example, cannabis typically produces lack of convergence, a raised pulse and normal or slightly enlarged pupils, while narcotic analgesics such as opioids typically produce very small pupils and a lowered pulse.
In Ohio, the drug recognition expert program is coordinated through the Ohio State Highway Patrol, and DREs must keep their certification current. Their testimony is usually admitted as that of a trained observer or expert, and Ohio courts have accepted DRE opinions together with toxicology to prove that a driver was under the influence of a drug of abuse.
Disclosure and the breath file
Every evidential test produces records that must be disclosed to the defense: the certificate or test record, the instrument's maintenance and calibration logs, the operator's qualifications, the observation notes and any video from the breath room. Ohio courts require prosecutors to provide records of the instrument's certification and calibration checks and the operator's permit, and defense lawyers routinely request them. Okoro keeps a copy of every test record with his notes. 'Somebody will ask for it,' he says. 'Every single time.'
Hospital samples and medical records
After serious collisions, drivers are often taken to hospital before police can arrange an evidential test, and hospital staff may take blood for medical reasons. Those medical samples and records can be valuable evidence, but they belong to the patient's medical care and are protected by privacy law. Police generally need a search warrant or subpoena to obtain hospital blood test results or medical records, which are protected by state law and by federal health privacy rules that allow disclosure to police only in limited situations, such as in response to a warrant or court order. Hospital tests also often measure alcohol in serum or plasma rather than whole blood, which gives a higher number; a toxicologist must convert the result before it can be compared with the legal limit.
The breath room as evidence
Most stations now record the breath room on video. The recording shows the observation period, the demand, the instructions and the samples, and it often settles disputes about what was said and whether the person had a chance to contact counsel. Okoro tells new officers to assume that a judge will watch every minute of the video. 'If you are on your phone during the observation period, the judge will see it. If you explain the instructions clearly and patiently, the judge will see that too.'
Electronic warrants have changed blood draws. A Port Ardent officer can now complete an affidavit on a laptop, send it to an on-call judge, answer questions by video and receive a signed warrant in fifteen to thirty minutes, at any hour. The officer must then record who drew the blood, when, using what kit, and how it was sealed, labeled and sent to the crime laboratory for analysis. Continuity is as important for a blood sample as for any other exhibit, and a gap in the record can make the result impossible to use. Ohio law also requires that blood be drawn by a physician, nurse, phlebotomist or other qualified person, not by the officer.
Common mistakes
MistakeMouth alcohol does not affect breath results.
InsteadIt can greatly raise a result, which is why officers observe the person before the test.
MistakeA breath sample is admissible however long after the arrest it was taken.
InsteadIt must be withdrawn within three hours under section 4511.19(D)(1)(b).
MistakePolice can always draw blood without a warrant after an OVI arrest.
InsteadBirchfield and McNeely require a warrant for blood unless there is a real emergency or valid consent.
MistakeA DRE identifies the exact drug.
InsteadThe DRE identifies drug categories; toxicology confirms the drug.
Summary and key terms
- Breath instruments measure deep lung air and report a concentration; observation guards against mouth alcohol.
- Samples must be within three hours and follow Ohio Department of Health rules; the lower result is reported.
- Blood alcohol rises, peaks and falls at a fairly steady elimination rate, which toxicologists use to estimate earlier concentrations.
- Blood generally requires a warrant (McNeely, Birchfield), with exceptions for real emergencies (Schmerber, Mitchell).
- Drug recognition experts follow a twelve-step evaluation and identify drug categories.
- Every test produces records that must be kept and disclosed.
- Mouth alcohol
- Alcohol in the mouth that can falsely raise a breath result.
- Elimination rate
- The rate at which the body removes alcohol from the blood.
- Drug recognition expert
- An officer trained to evaluate whether a person is impaired by drugs and by which category.
- Evidential breath instrument
- An instrument certified by the Ohio Department of Health for evidential breath tests.
Practice problems
Work each problem on paper first, then reveal the answer to check.
Why is there an observation period before a breath test?
Show answer
To make sure mouth alcohol from burping, vomiting or anything in the mouth does not affect the result.
What is the time limit for withdrawing a sample in Ohio?
Show answer
Three hours from the alleged violation.
What does a DRE's opinion identify?
Show answer
Whether the person is impaired and by which drug category or categories.
What range of elimination rates do toxicologists commonly use?
Show answer
About 0.010 to 0.020 per hour.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.