
HSE-223 · Lesson 12 of 12 · 30 min
Managing risk assessments, human factors and capstone: a chemical storage workshop
The methods in this course are only as good as the system around them. A brilliant HAZOP filed in a cabinet, a bowtie whose critical controls are never checked, or a JHA written by someone who has never seen the job will not prevent a single injury. This final lesson looks at how organizations manage risk assessments as a system: competence, team composition, quality review, records, revalidation and links to management of change. It then looks at the human and organizational factors that make assessments fail, and finishes with a capstone workshop that applies several methods to one realistic case: a chemical storage and dispensing building.
Risk assessment as a managed system
ISO 45001 clause 6.1.2 and ISO 31000 both treat risk assessment as a continuing process, not a one-off event. A mature organization has a written procedure that says which methods are used for which situations, who may lead each type of study, how teams are formed, how results are recorded and approved, how recommendations are tracked, and when assessments must be reviewed. It keeps a register of its significant risks and assessments, so that managers can see which assessments are current, which are overdue and which recommendations remain open.
| Element | What good looks like |
|---|---|
| Procedure | States methods for each situation, escalation rules and approval levels |
| Competence | Defined training and experience for facilitators and team members; records kept |
| Team composition | Operations, maintenance, engineering and safety, plus workers who do the job |
| Quality review | Independent check of significant studies before approval |
| Recommendation tracking | Owners, dates, status reporting, documented rejection with reasons |
| Review triggers | Change, incident, new information, and a set interval |
| Records | Searchable register linked to drawings, procedures and permits |
| Verification | Field checks that controls and critical barriers are in place |
In Canada, CSA Z1002 and CSA Z1000 describe these elements for occupational risks, and CSA Z767 adds them for process safety, including hazard analysis revalidation, management of change and pre-start-up review. Joint health and safety committees and representatives have a legal role in hazard identification in every jurisdiction and should participate in significant assessments.
Competence and team composition
Different methods need different competence. Anyone trained can contribute to a JHA, but a HAZOP needs a trained, experienced facilitator; LOPA and SIL work need people competent under IEC 61511; and QRA needs specialists in consequence modelling and reliability. Good practice is to define the competence required for each role in the procedure, to keep records of training and experience, and to use independent facilitators for major studies so that the design team does not mark its own homework. Diversity matters too: teams that include operators, maintainers, contractors and, where relevant, people with different backgrounds identify more scenarios.
Human and organizational factors in risk assessment
Assessments fail for human reasons as often as technical ones. Groupthink makes a team converge too early on a comfortable answer, especially when a senior person speaks first. Anchoring makes the first number suggested stick, even if it was a guess. Optimism bias leads people to underestimate the likelihood of failures in systems they designed or operate. Normalization of deviance, a term from sociologist Diane Vaughan's study of the Challenger disaster, describes how repeated small departures from standards become accepted as normal because nothing bad has happened yet. And production pressure can push teams to finish quickly or to rate risks lower to avoid costly recommendations.
Facilitators counter these with technique. They ask junior members and workers for their views first, before senior people speak. They ask the team to estimate independently before discussing. They use data and anchors to check likelihood estimates. They challenge assumptions explicitly: "What would have to be true for this to happen?" They record dissenting views. And they make sure the study is given enough time; a HAZOP that is squeezed into half its proper duration will miss things.
Organizational factors shape the whole system. The Chemical Safety Board's investigation of the 2005 Texas City refinery explosion and the Baker Panel review found that risk assessments existed but had not addressed the siting of temporary trailers near the isomerization unit, that management of change was weak and that process safety performance was measured by personal injury rates, which were good. In Canada, the Lac-Mégantic rail disaster of 2013 showed how risk assessments of single-person train crews and securement practices failed to anticipate a catastrophic combination of events. Both cases show that assessment quality depends on leadership, resources and the willingness to hear bad news.
Worked problem
Spotting bias in a workshop
In a what-if review of a new solvent transfer, the plant manager opens by saying, "This is the same design we use at our other site, and we've never had a problem." The team then rates every scenario as unlikely, and no one mentions that the other site had a near miss with static ignition last year. Identify the biases and what the facilitator should do.
Show solution
- Anchoring and authority: the manager's opening statement sets the expectation before the team thinks independently.
- Optimism bias and normalization of deviance: "never had a problem" ignores a near miss that shows the scenario is credible.
- Facilitator actions: ask team members to list scenarios independently before discussion; bring incident and near-miss data from both sites; ask specifically about static and ignition; record the near miss as evidence for the likelihood rating.
Answer: Anchoring, authority influence, optimism bias and normalization of deviance; use independent input and incident data.
Revalidation and change
Assessments go out of date. Equipment is modified, procedures change, staff turn over, new knowledge emerges and incidents reveal scenarios that were missed. Management of change should trigger review of the relevant assessment before any change is made. Periodic revalidation, every five years for PSM PHAs in the US and at a similar interval in most company standards elsewhere, checks that the whole assessment still reflects the facility. A revalidation is not a rubber stamp: it should review all changes and incidents since the last study, check whether recommendations were implemented and effective, and consider new knowledge such as updated failure data or lessons from industry incidents.
Capstone workshop: the case
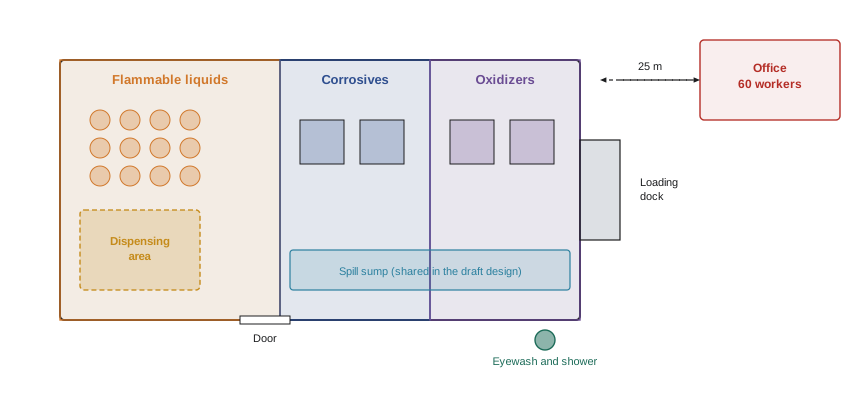
A manufacturer is building a new chemical storage and dispensing building. It will hold flammable liquids (toluene and isopropyl alcohol in 205-litre drums, up to 40 drums), corrosives (sulphuric acid and sodium hydroxide solution in 1,000-litre totes, up to 6 totes) and oxidizers (sodium hypochlorite, up to 4 totes). Operators will dispense toluene from drums into 20-litre safety cans for the production area, about 30 times a week. An office building with 60 workers is 25 metres away. The company asks for a risk assessment before construction is complete, to confirm that the design is adequate and to identify any changes.
Step 1: choose the methods
Following Lesson 2, the team starts simple and escalates. A checklist based on the fire code and the company's chemical storage standard checks segregation, ventilation, electrical classification, containment and emergency equipment. A what-if review covers deliveries, storage and abnormal events. A JHA covers the dispensing task. Scenarios with potential fatalities go to a simple LOPA. A bowtie for the top event "loss of containment of flammable liquid in the building" is prepared for operators and managers, and its critical controls are added to the site's verification program. A full QRA is not justified for this inventory, but the team checks the separation distance to the office.
Worked problem
Checklist findings
The checklist review finds: (1) the corrosives and oxidizer bays share a single spill sump; (2) the dispensing area has no bonding and grounding points; (3) the eyewash is 25 metres from the corrosives bay, through a door; (4) ventilation is designed but no rate has been confirmed for the dispensing area. For each, identify the hazard and recommend an action.
Show solution
- (1) Acid and hypochlorite mixing in a shared sump can release chlorine gas. Separate the sumps or provide separate containment for each bay.
- (2) Static discharge during toluene transfer can ignite vapour. Install bonding and grounding points with clamps and a procedure, and verify continuity.
- (3) An eyewash 25 metres away through a door does not meet the usual guidance of reaching it within about 10 seconds on an unobstructed path (ANSI/ISEA Z358.1). Add an eyewash and shower in or beside the corrosives bay.
- (4) Confirm the dispensing ventilation rate meets the fire code and keeps vapour well below the lower flammable limit and the occupational exposure limit; consider local exhaust at the dispensing point.
Answer: Separate the sumps, add bonding and grounding, relocate the eyewash and shower, and confirm the ventilation.
Step 2: what-if and JHA
The what-if review asks questions such as: What if a drum is punctured by a forklift? What if the wrong tote is delivered to the oxidizer bay? What if the ventilation fan fails during dispensing? What if a fire starts in the flammable bay while the office is occupied? The JHA for dispensing breaks the task into steps: move the drum to the dispensing station, bond and ground, open the bung, fit the pump, dispense to the safety can, close and label, return the drum. Energy-based hazards at each step include gravity (drum handling), chemical (vapour and splash) and fire (static ignition).
Worked problem
Simple LOPA for a dispensing fire
Scenario: operator fails to attach the bonding clamp (human error, 0.01 per task); static discharge ignites toluene vapour (conditional probability 0.1 given no bonding, because ignition also needs a flammable mixture and sufficient charge); a flash fire injures or kills the operator (probability of fatality 0.5). The task is done 30 times a week for 50 weeks a year. IPL: a bonding verification interlock that prevents the pump from running unless continuity is confirmed (PFD 0.1). Target: \( 10^{-5} \) per year for a fatality. Calculate the frequency with and without the interlock.
Show solution
- Tasks per year: \( 30 \times 50 = 1{,}500 \).
- Initiating frequency: \( 1{,}500 \times 0.01 = 15 \) missed bonds per year.
- Without interlock: \( 15 \times 0.1 \times 0.5 = 0.75 \) per year. This is far above the target.
- With interlock: \( 0.75 \times 0.1 = 0.075 \) per year, still far above \( 10^{-5} \).
- The numbers show the design itself needs to change: closed transfer systems, conductive equipment, inerting or a pump system with integral bonding would reduce both the initiating frequency and the chance of ignition. This is a case for inherent safety, not just more layers.
Answer: About 0.75 per year without and 0.075 per year with the interlock; both far exceed \( 10^{-5} \), so the dispensing design must change.
The result looks alarming, and it should be examined: are the probabilities realistic? Many real dispensing operations have fewer fires than this suggests, partly because not every missed bond produces a spark in a flammable mixture. But even if the estimates are ten or a hundred times too high, the risk remains well above the target. The lesson for the team is that a frequent manual task with a high-energy hazard needs engineering and inherent safety solutions, and that LOPA is useful precisely because it makes this visible.
Step 3: bowtie and critical controls
The bowtie for loss of containment of flammable liquid shows threats (forklift puncture, drum corrosion, overfilling the safety can, valve or pump leak) and consequences (pool fire, flash fire, vapour exposure, fire spreading to the office). Prevention barriers include forklift-free zones and drum racks with impact protection; mitigation barriers include spill containment, fire suppression, gas detection with ventilation interlock and a fire separation wall facing the office. The team selects four critical controls: bonding with interlock, spill containment, fire suppression and the fire separation. Each gets a performance standard, an owner and a monthly field verification.
Step 4: report and follow-up
The final report states the scope, methods and team; lists the findings and recommendations with owners and dates; records the risk before and after recommendations; identifies the critical controls and how they will be verified; and states the limits of the study, such as that it did not model off-site toxic dispersion from a chlorine release. It is reviewed independently, approved by the responsible manager and entered in the risk register. A pre-start-up safety review confirms the recommendations are complete before chemicals are brought in.
Common mistakes
MistakeTreating a risk assessment as a one-time document.
InsteadManage assessments as a system with review triggers, tracking and verification.
MistakeLetting the most senior person speak first in a workshop.
InsteadGather independent views first, especially from workers and junior members.
MistakeAccepting "never had a problem" as evidence.
InsteadCheck near-miss and industry data; absence of incidents is not proof of safety.
MistakeAdding layer after layer to a frequent high-energy task.
InsteadLook for inherent safety and design changes first.
MistakeRevalidating by copying the old study.
InsteadReview changes, incidents, recommendation effectiveness and new knowledge.
Summary and key terms
- Risk assessment works only as a managed system with procedures, competence and tracking.
- Different methods need different competence; use independent facilitators for major studies.
- Groupthink, anchoring, optimism bias and normalization of deviance undermine assessments.
- Facilitators counter bias with independent input, data and explicit challenge.
- Management of change and periodic revalidation keep assessments current.
- The capstone combined checklist, what-if, JHA, LOPA and bowtie on one storage building.
- Frequent high-energy manual tasks often need inherent safety rather than more layers.
- Risk register
- A record of significant risks, assessments and their status.
- Revalidation
- Formal periodic review of an existing assessment.
- Groupthink
- A team converging on an answer without critical evaluation.
- Anchoring
- Over-reliance on the first number or idea suggested.
- Optimism bias
- Underestimating the likelihood of bad outcomes.
- Normalization of deviance
- Gradual acceptance of departures from standards because nothing bad has happened.
- Inherent safety
- Reducing hazards by design, such as smaller inventories or safer materials.
- Bonding and grounding
- Connecting containers electrically and to earth to prevent static discharge.
- Pre-start-up safety review
- A check that a new or changed facility is ready to operate safely.
- Independent review
- A check of a study by competent people not involved in producing it.
Practice problems
Work each problem on paper first, then reveal the answer to check.
Name four elements of a managed risk assessment system.
Show answer
Procedure, competence, team composition, quality review, tracking, review triggers, records, verification.
Why use an independent facilitator for a major study?
Show answer
So the design team does not mark its own homework.
What is anchoring?
Show answer
Over-reliance on the first number suggested.
Who coined the term normalization of deviance?
Show answer
Diane Vaughan, in her study of the Challenger disaster.
Give two triggers for reviewing an assessment.
Show answer
A change, an incident, new information, or a set interval.
Why is a shared sump for acid and hypochlorite dangerous?
Show answer
Mixing can release chlorine gas.
A task is done 20 times a week for 50 weeks with an error probability of 0.01. What is the initiating frequency?
Show answer
10 per year.
What does a LOPA result far above target for a frequent manual task suggest?
Show answer
The design needs to change toward inherent safety.
Name two critical controls from the capstone.
Show answer
Bonding with interlock, spill containment, fire suppression, fire separation.
What should a revalidation review?
Show answer
Changes, incidents, recommendation effectiveness and new knowledge.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.