
BIOL-450 · Lesson 4 of 12 · 25 min
Genome instability and DNA repair
Every human cell suffers tens of thousands of DNA lesions a day: bases lost to spontaneous hydrolysis, bases oxidized by the by-products of metabolism, mismatches left by DNA polymerase, and the occasional double-strand break. A network of repair pathways fixes almost all of them. Cancer cells typically carry thousands to hundreds of thousands of mutations, plus large-scale rearrangements and changes in chromosome number. Lesson 1 called this genome instability an enabling characteristic: it does not make a cell grow, but it speeds the acquisition of changes that do. This lesson looks at the main repair pathways, what happens when they fail, how the scars of past damage can be read as mutational signatures, and how repair defects become therapeutic targets.
Sources of DNA damage
Damage comes from inside and outside the cell. Endogenous sources include depurination, deamination of cytosine to uracil and of 5-methylcytosine to thymine (the most common source of mutations in human tissues, which accumulates steadily with age), reactive oxygen species that produce 8-oxoguanine, and errors and stalled forks during replication. Exogenous sources include ultraviolet light, which links adjacent pyrimidines into cyclobutane dimers; tobacco carcinogens such as benzo[a]pyrene, whose metabolites form bulky adducts on guanine; aflatoxin from moulds on stored grain; ionizing radiation, which causes strand breaks; and chemotherapy drugs that are designed to damage DNA. Whether damage becomes a mutation depends on whether it is repaired correctly before the cell replicates.
The main repair pathways
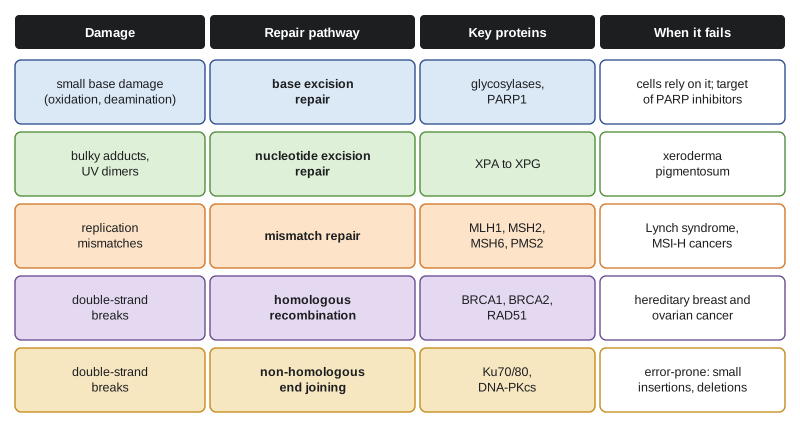
Base excision repair removes small, non-distorting base lesions. A glycosylase cuts out the damaged base, an endonuclease nicks the backbone, and polymerase β and ligase fill the gap. PARP1 detects single-strand breaks and recruits repair proteins, a role central to the story of synthetic lethality below. Nucleotide excision repair removes bulky, helix-distorting lesions such as UV dimers and tobacco adducts, cutting out a stretch of about 30 nucleotides. Inherited defects in it cause xeroderma pigmentosum, with extreme sensitivity to sunlight and skin cancer rates more than a thousand times normal at young ages. Mismatch repair corrects base mismatches and small insertion-deletion loops left by replication, using MSH2–MSH6 and MSH2–MSH3 to recognize errors and MLH1–PMS2 to direct their removal.
Double-strand breaks are the most dangerous lesions, because both strands are cut. Two pathways repair them. Non-homologous end joining ligates the broken ends directly; it works throughout the cell cycle but can delete or add a few bases. Homologous recombination uses the intact sister chromatid as a template and restores the original sequence; it works only in S and G2 phase, after replication. BRCA1 helps commit breaks to homologous recombination by promoting resection of the ends, and BRCA2 loads RAD51 onto the single-stranded DNA so it can invade the sister. A backup, microhomology-mediated end joining, depends on polymerase θ and leaves characteristic deletions flanked by short repeated sequences.
Mismatch repair deficiency and microsatellite instability
Microsatellites are short tandem repeats, such as a run of A bases or a CA dinucleotide repeated 20 times. During replication the polymerase can slip on them, adding or removing a repeat unit. Mismatch repair normally fixes these loops. When it fails, microsatellites change length throughout the genome, a state called microsatellite instability (MSI), and the mutation rate rises 100- to 1,000-fold. Tumours with mismatch repair deficiency (dMMR) or high microsatellite instability (MSI-H) carry very many mutations, especially frameshifts in coding repeats, which inactivate genes such as TGFBR2 and BAX.
About 15 per cent of colorectal cancers are MSI-H. A minority result from Lynch syndrome, the inherited form introduced with Daniel's family in lesson 3, caused by germline variants in MLH1, MSH2, MSH6, PMS2 or deletions affecting EPCAM. Most sporadic MSI-H colorectal cancers arise instead from methylation of the MLH1 promoter, often with a BRAF V600E mutation, which helps distinguish sporadic from inherited cases. Testing every colorectal and endometrial cancer for mismatch repair status, by immunohistochemistry for the four proteins or by an MSI test, is now standard in many centres. It identifies families with Lynch syndrome and, as lesson 10 shows, patients likely to respond to immune checkpoint inhibitors, because the many mutations produce abnormal peptides that the immune system can recognize.
Chromosomal instability
Most solid tumours are aneuploid: they have abnormal numbers of chromosomes, often with gains and losses of whole arms and many structural rearrangements. Chromosomal instability (CIN) is the ongoing tendency to gain and lose chromosomes at division, caused by defects in the spindle assembly checkpoint, abnormal centrosome numbers, merotelic kinetochore attachments, or replication stress that leaves under-replicated regions to break in mitosis. CIN generates diversity for selection to act upon, and the loss of chromosome arms is a common route to the second hit of a tumour suppressor. Whole genome doubling, in which a cell duplicates its entire genome without dividing, occurs in roughly a third of advanced tumours and buffers the cell against the harmful effects of later chromosome losses.
Sequencing has revealed even more dramatic events. In chromothripsis, described in 2011, one or a few chromosomes shatter into many pieces in a single catastrophe and are stitched back together in random order, often after being trapped in a micronucleus outside the main nucleus. Extrachromosomal DNA, circular pieces of DNA carrying amplified oncogenes such as MYC or EGFR, is found in a substantial share of tumours and is unequally partitioned at division, allowing copy number to change rapidly from cell to cell.
Telomeres and replicative immortality
Linear chromosomes shorten each time DNA is copied, because the replication machinery cannot complete the lagging strand at the very end. Telomeres, long arrays of the repeat TTAGGG capped by the shelterin protein complex, buffer this loss. In most human somatic cells, telomeres shorten by about 50 to 100 base pairs per division until they become critically short and trigger a DNA damage response, halting division after roughly 40 to 60 doublings in culture, the Hayflick limit. Cells that evade this checkpoint, for instance by losing p53 and RB, keep dividing until telomeres fail completely, chromosomes fuse end to end and break again in mitosis, a crisis that fuels chromosomal instability.
Escaping crisis requires restoring telomeres. About 85 to 90 per cent of cancers reactivate telomerase, the reverse transcriptase TERT with its RNA template, often through mutations in the TERT promoter that create new binding sites for transcription factors. TERT promoter mutations are among the most common non-coding mutations in cancer, found in most glioblastomas, many melanomas and bladder cancers. The remaining tumours use alternative lengthening of telomeres (ALT), a recombination-based mechanism frequently associated with loss of ATRX or DAXX. Elizabeth Blackburn, Carol Greider and Jack Szostak received the 2009 Nobel Prize in Physiology or Medicine for discovering how telomeres and telomerase protect chromosomes.
Mutational signatures
Each mutational process leaves a characteristic pattern. Mutations can be classified by the base change (six classes, such as C to T) and the bases immediately before and after, giving 96 trinucleotide contexts. Ludmil Alexandrov, Michael Stratton and colleagues showed in 2013 that the mutation counts of thousands of tumours could be decomposed into a few dozen recurrent signatures, using non-negative matrix factorization. Some signatures have known causes: SBS1, C to T at CpG sites, reflects deamination of methylated cytosine and accumulates with age; SBS4 reflects tobacco smoke; SBS7 reflects ultraviolet light; SBS2 and SBS13 reflect APOBEC cytidine deaminases; SBS3 reflects homologous recombination deficiency; and signatures 6, 15, 26 and 44 reflect mismatch repair deficiency. The COSMIC catalogue lists the current set. Signatures turn a tumour's genome into a record of its history and can identify repair defects that matter for treatment.
# Toy mutational signature analysis: factor tumour mutation counts into signatures with NMF.
import numpy as np
rng = np.random.default_rng(4)
contexts = 12                                    # a compressed set of mutation contexts (illustrative)
S = np.array([                                   # three invented signatures, each sums to 1
    [.30, .25, .20, .10, .05, .04, .02, .01, .01, .01, .005, .005],   # 'ageing-like'
    [.01, .02, .03, .05, .30, .30, .15, .08, .03, .01, .01, .01],     # 'tobacco-like'
    [.08, .08, .08, .08, .08, .09, .09, .09, .08, .08, .085, .085]])  # 'flat, HR-deficiency-like'
expo = rng.gamma(2, [[400, 50, 30]] * 20) * (rng.random((20, 3)) < 0.7)  # 20 tumours
counts = rng.poisson(expo @ S)
k = 3
W = rng.random((counts.shape[0], k)) + 0.1; H = rng.random((k, contexts)) + 0.1
for _ in range(3000):                            # Lee-Seung multiplicative updates (KL divergence)
    WH = W @ H + 1e-9
    H *= (W.T @ (counts / WH)) / W.sum(0)[:, None]
    WH = W @ H + 1e-9
    W *= ((counts / WH) @ H.T) / H.sum(1)[None, :]
scale = H.sum(1); H /= scale[:, None]; W *= scale[None, :]
match = [int(np.argmax([np.dot(h, s) / np.linalg.norm(h) / np.linalg.norm(s) for s in S])) for h in H]
for j, m in enumerate(match):
    cos = np.dot(H[j], S[m]) / np.linalg.norm(H[j]) / np.linalg.norm(S[m])
print(f"recovered signature {j} best matches true signature {m} (cosine similarity {cos:.3f})")recovered signature 0 best matches true signature 1 (cosine similarity 0.998) recovered signature 1 best matches true signature 2 (cosine similarity 0.892) recovered signature 2 best matches true signature 0 (cosine similarity 0.999)
The two peaked signatures are recovered almost perfectly; the flat one, which resembles the featureless signature of homologous recombination deficiency, is recovered less well, because a flat pattern is easy to confuse with mixtures of the others. That is a real problem in practice, and one reason flat signatures are assigned cautiously. Real analyses use the full 96 contexts, hundreds to thousands of genomes and careful statistics to decide how many signatures are present, but the principle is the same: mutation counts are modelled as non-negative mixtures of non-negative signatures, and each tumour's exposure to each process is estimated.
Synthetic lethality and PARP inhibitors
Two genes are synthetically lethal when losing either alone is tolerated but losing both kills the cell. The idea, borrowed from yeast genetics, offers a way to kill cancer cells that have lost a tumour suppressor, something that cannot be targeted directly because the protein is gone. BRCA-deficient cells cannot repair double-strand breaks by homologous recombination. Inhibiting PARP traps PARP1 on DNA at single-strand breaks; when replication forks hit these trapped complexes, they collapse into double-strand breaks. Normal cells repair them by homologous recombination; BRCA-deficient cells cannot and die. Two groups, led by Alan Ashworth and Thomas Helleday, reported this in 2005.
PARP inhibitors such as olaparib, niraparib, rucaparib and talazoparib are now used for BRCA-mutant ovarian, breast, prostate and pancreatic cancers, and for tumours with other homologous recombination defects. Their effectiveness confirms the principle, and their limits illustrate resistance: tumours can restore homologous recombination by secondary mutations that put BRCA2 back in frame, or by losing other proteins such as 53BP1 that block resection. Polymerase θ inhibitors, which target the backup pathway that HR-deficient cells lean on, are in clinical trials.
# Synthetic lethality: viability of cells by genotype and PARP inhibitor (illustrative values).
viability = {   # fraction of colony-forming cells surviving
    ('BRCA2 normal', 'no drug'): 1.00, ('BRCA2 normal', 'PARP inhibitor'): 0.85,
    ('BRCA2 lost', 'no drug'): 0.90,   ('BRCA2 lost', 'PARP inhibitor'): 0.02,
    ('BRCA2 lost + reversion', 'no drug'): 0.92, ('BRCA2 lost + reversion', 'PARP inhibitor'): 0.80}
for (geno, drug), v in viability.items():
    bar = '#' * round(v * 40)
    print(f"{geno:24s} {drug:15s} {v:4.2f} {bar}")
sel = viability[('BRCA2 normal', 'PARP inhibitor')] / viability[('BRCA2 lost', 'PARP inhibitor')]
print(f"selective killing of BRCA2-lost cells: about {sel:.0f}-fold; a reversion mutation removes it")BRCA2 normal no drug 1.00 ######################################## BRCA2 normal PARP inhibitor 0.85 ################################## BRCA2 lost no drug 0.90 #################################### BRCA2 lost PARP inhibitor 0.02 # BRCA2 lost + reversion no drug 0.92 ##################################### BRCA2 lost + reversion PARP inhibitor 0.80 ################################ selective killing of BRCA2-lost cells: about 42-fold; a reversion mutation removes it
| Repair defect | Genomic scar | Inherited syndrome | Therapeutic implication |
|---|---|---|---|
| Mismatch repair (MLH1, MSH2, MSH6, PMS2) | MSI-H, very high mutation burden, frameshifts | Lynch syndrome | Immune checkpoint inhibitors |
| Homologous recombination (BRCA1, BRCA2, PALB2) | SBS3, deletions with microhomology, large-scale state transitions | Hereditary breast and ovarian cancer | PARP inhibitors, platinum drugs |
| Nucleotide excision repair | UV or adduct signatures | Xeroderma pigmentosum | Sensitivity to cisplatin in some tumours |
| Polymerase ε proofreading (POLE) | Ultra-high mutation burden, specific signatures | Polymerase proofreading-associated polyposis | Good prognosis, immunotherapy response |
| Telomere maintenance (TERT, ATRX) | TERT promoter mutation or ALT | Rare telomere disorders | Telomerase and ALT as research targets |
Worked problem
Interpreting a mismatch repair result
Daniel's colorectal tumour shows loss of MSH2 and MSH6 protein staining, with normal MLH1 and PMS2. His germline test found an MSH2 variant. A second patient's tumour shows loss of MLH1 and PMS2 staining, a BRAF V600E mutation and MLH1 promoter methylation. Classify each tumour.
Show solution
- MSH2 and MSH6 work as a pair, so MSH6 is lost when MSH2 is absent; with a germline MSH2 variant, Daniel's tumour is Lynch syndrome-associated.
- In the second patient, MLH1 loss with promoter methylation and BRAF V600E points to sporadic silencing of MLH1.
- Both tumours are mismatch repair deficient and likely MSI-H, with high mutation burdens.
- Only Daniel's family needs cascade genetic testing; both patients may benefit from immune checkpoint inhibitors if their cancers progress.
Answer: Daniel's tumour is Lynch syndrome-associated dMMR; the second is sporadic dMMR caused by MLH1 promoter methylation.
Common mistakes
MistakeThinking repair defects cause cancer by making cells grow faster.
InsteadCaretaker defects raise the mutation rate, which speeds acquisition of the changes that drive growth.
MistakeTreating all MSI-H colorectal cancers as Lynch syndrome.
InsteadMost sporadic cases arise from MLH1 promoter methylation, often with BRAF V600E.
MistakeAssuming PARP inhibitors work on any cancer.
InsteadThey exploit homologous recombination deficiency, so benefit depends on BRCA or related defects.
MistakeCalling telomerase activity unique to cancer.
InsteadStem cells and germ cells express telomerase; most somatic cells do not.
MistakeReading a mutational signature as a single gene mutation.
InsteadA signature reflects a process, such as tobacco exposure or loss of a repair pathway, acting over time.
Summary and key terms
- Cells suffer constant DNA damage from endogenous and exogenous sources; repair pathways fix almost all of it.
- Base excision, nucleotide excision, mismatch repair, homologous recombination and non-homologous end joining handle different lesions.
- Mismatch repair loss causes microsatellite instability and very high mutation burdens, inherited in Lynch syndrome or caused by MLH1 methylation.
- Chromosomal instability, whole genome doubling, chromothripsis and extrachromosomal DNA reshape cancer genomes.
- Cancers overcome telomere shortening by reactivating telomerase, often through TERT promoter mutations, or by ALT.
- Mutational signatures, extracted by non-negative matrix factorization, record the processes that shaped a tumour.
- Synthetic lethality between BRCA loss and PARP inhibition turned a repair defect into a treatment target.
- genome instability
- An increased tendency of the genome to acquire mutations or chromosomal changes.
- mismatch repair
- The pathway that corrects replication mismatches and small insertion-deletion loops.
- microsatellite instability
- Changes in the length of short tandem repeats throughout the genome due to mismatch repair loss.
- homologous recombination
- Error-free repair of double-strand breaks using the sister chromatid as a template.
- non-homologous end joining
- Direct ligation of broken DNA ends, which can add or delete bases.
- chromosomal instability
- An ongoing high rate of gain and loss of whole chromosomes or large chromosome segments.
- chromothripsis
- Shattering of one or a few chromosomes and random reassembly in a single event.
- telomerase
- A reverse transcriptase that adds telomere repeats to chromosome ends.
- mutational signature
- A characteristic pattern of mutations produced by a particular mutational process.
- synthetic lethality
- A relationship in which loss of either of two genes is tolerated but loss of both is lethal.
- PARP inhibitor
- A drug that blocks and traps PARP enzymes on DNA, lethal to cells lacking homologous recombination.
Practice problems
Work each problem on paper first, then reveal the answer to check.
Which repair pathway fixes UV-induced pyrimidine dimers?
Show answer
Nucleotide excision repair.
Why is homologous recombination limited to S and G2 phase?
Show answer
It needs the sister chromatid as a template, which exists only after replication.
What causes most sporadic MSI-H colorectal cancers?
Show answer
Methylation of the MLH1 promoter.
Why are dMMR tumours often responsive to immunotherapy?
Show answer
Their many mutations produce abnormal peptides that T cells can recognize.
How do most cancers overcome telomere shortening?
Show answer
By reactivating telomerase, often through TERT promoter mutations.
What does a mutational signature with many C to T changes at CpG sites suggest?
Show answer
Spontaneous deamination of methylated cytosine, which accumulates with age.
Explain why PARP inhibitors kill BRCA-deficient cells selectively.
Show answer
Trapped PARP causes replication-associated double-strand breaks that only homologous recombination can repair.
Give one mechanism of resistance to PARP inhibitors.
Show answer
A secondary mutation restoring BRCA2 function, or loss of 53BP1 restoring resection.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.