
LES-216 · Lesson 9 of 12 · 20 min
Stop the dying: rescue, medical care and working with EMS
▶ Video coming soon A video version of this lesson is on the way.
At 08:55, three minutes after the first officers entered Harbor Point Mall, the controller declared the attacker stopped. Fourteen role players lay in the food court and the corridors with moulage wounds: bright red stains, realistic gunshot injuries, and cards telling them how to act and how long they would survive without care. One card read: 'Gunshot wound to the upper thigh, heavy bleeding. Without a tourniquet, you lose consciousness at 09:02 and die at 09:06.' The officers who stopped the attacker were on the far side of the food court. The paramedics were outside in the parking lot. Desjardins asks the class the question the exercise was built around. 'How do you get a paramedic to that person, or get that person to a paramedic, in the next eleven minutes, in a building where you are not yet sure there is no second attacker?'
This lesson covers the second priority on an active threat, stop the dying, and the medical side of every high-risk call. It explains why bleeding control comes first, how the old rule that paramedics wait outside until the whole building is secure has changed, how police and paramedics work together in rescue task forces, and how the wounded are triaged, moved and transported. Medical techniques are taught in first aid and tactical casualty care courses and are described here only at the level of principle.
Why bleeding control comes first
Studies of military and civilian casualties have found that uncontrolled bleeding from the arms and legs is one of the leading preventable causes of death after gunshot and blast injuries. A person can bleed to death from a severe limb wound in a few minutes, far faster than an ambulance can usually arrive and long before the scene of an active threat is fully secure. Controlling that bleeding with direct pressure, wound packing or a tourniquet can save a life with simple equipment and a few minutes of training.
For many years, tourniquets were taught as a last resort in civilian first aid because of fears that they would cause the loss of limbs. Experience in Iraq and Afghanistan showed that properly applied commercial tourniquets save lives and rarely cause lasting harm when used for a few hours. That evidence changed civilian practice. After the shooting at Sandy Hook Elementary School in Newtown, Connecticut, in December 2012, the American College of Surgeons convened a group of experts whose recommendations, known as the Hartford Consensus, called for police officers and the public to be trained and equipped to control bleeding. The Stop the Bleed campaign, launched in 2015, now trains members of the public in both countries.
| Letter | Priority |
|---|---|
| T | Threat suppression |
| H | Hemorrhage control |
| RE | Rapid extrication to safety |
| A | Assessment by medical providers |
| T | Transport to definitive care |
The THREAT priorities follow the same order as the police priorities in lesson 8. First the threat is stopped. Then bleeding is controlled, people are moved to safety, medical providers assess them and they are taken to hospital. Desjardins points out that the spelling hemorrhage in the table is the American one used in the Hartford Consensus itself.
Officers as the first medical responders
On an active threat and on many other high-risk calls, police officers are the first people with any training to reach the wounded. Many services now issue every officer an individual first aid kit with a tourniquet, packing gauze and a pressure bandage, carried on the body or in the car, and train officers in tactical casualty care. The officers who stop the attacker are not usually the ones who give this care, but the next officers to arrive often are, and so are officers who reach an injured colleague or bystander on any call.
At Harbor Point Mall, the second pair of officers arrived at 08:56. Under the plan, they did not join the first pair but went to the wounded in the food court. Within four minutes they had applied tourniquets to three role players with limb wounds and moved two others who could walk to a corner of the food court away from the windows. They broadcast the number and location of the wounded to the command post. The role player whose card said he would die at 09:06 had a tourniquet on at 08:59.
U.S. agencies have adopted the same approach. Many agencies issue tourniquets to patrol officers and train them in Tactical Emergency Casualty Care, the civilian guidelines developed by the Committee for Tactical Emergency Casualty Care. Ohio's Good Samaritan law, in section 2305.23 of the Revised Code, protects people who give emergency care in good faith without pay from civil liability except for willful or wanton misconduct, and officers giving care as part of their duties are usually also covered by their agency.
Zones on an active threat
Active threat incidents are often described in three zones. The hot zone is where there is a direct, immediate threat, such as the area where the attacker is or might be. Only officers working to stop the threat go there. The warm zone is an area that officers have passed through or cleared but that is not yet fully secure, because there may be another attacker or a hidden hazard. Medical care and rescue can happen in the warm zone with police protection. The cold zone is outside, where the command post, staging, triage, treatment and transport areas are set up.
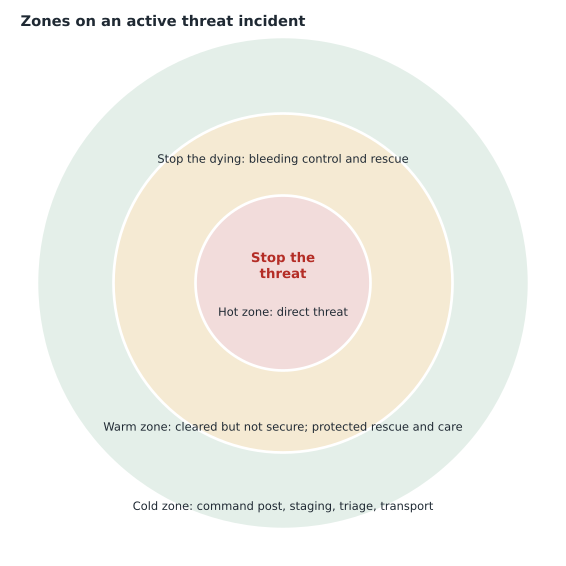
The zones are not fixed lines on a map. They change as officers move, as the threat is stopped and as information arrives. A corridor that was a hot zone at 08:53 became a warm zone at 08:55 when the attacker was stopped, and could have become hot again if a second attacker had appeared. That is why the command post must keep track of the zones and broadcast changes, and why everyone in the warm zone needs police protection.
Rescue task forces
The old rule in many places was that paramedics and firefighters stayed outside until police declared the whole scene secure. In a large building, that could take an hour or more, as it did at Columbine. The rescue task force was developed to change that. A rescue task force is a small team of paramedics or firefighters with protective equipment, escorted by police officers, that enters the warm zone to treat the wounded and bring them out while the rest of the building is still being searched. The concept was developed by the Arlington County Fire Department in Virginia with local police in the early 2010s and has spread widely in both countries.
At Harbor Point Mall, the first rescue task force of two paramedics, two firefighters and two officers entered at 09:04, nine minutes after the attacker was stopped, through the entrance closest to the food court. They found the wounded the second pair of officers had already treated, checked the tourniquets, triaged everyone and began bringing out the most seriously hurt. The first patient reached an ambulance at 09:11. A second rescue task force entered at 09:09 to reach two role players in a store corridor. By 09:32, all fourteen were out.
| Time | Event |
|---|---|
| 08:47 | Call received |
| 08:52 | First officers enter |
| 08:55 | Attacker stopped |
| 08:56 | Second officers begin bleeding control |
| 08:59 | Tourniquet on the most critical role player |
| 09:04 | First rescue task force enters |
| 09:11 | First patient in an ambulance |
| 09:32 | All fourteen wounded out |
Triage, casualty collection and transport
When there are many wounded, responders cannot treat everyone at once. Triage is the process of sorting the wounded by how urgently they need care, so that the people whose lives can be saved with quick care get it first. Many paramedic services use a system such as START, which sorts people into immediate, delayed, minor and expectant groups using simple checks of walking, breathing, circulation and responsiveness. Responders often set up a casualty collection point, a protected place in or near the warm zone where the wounded are gathered for treatment and transport. Transport is coordinated so that the most seriously injured go to the trauma center and hospitals are not overwhelmed.
Port Ardent's nearest Level I trauma center is twenty-five minutes away by ambulance. During the exercise, the city's EMS service sent the five patients triaged as immediate to the trauma center and the others to two community hospitals, and notified all three before the first patient left. In Ohio, regional trauma systems and hospital preparedness coalitions plan for mass casualty incidents, and hospitals run their own plans for receiving many patients at once.
The public as immediate responders
Because most active threat incidents are over within minutes, the people already at the scene are the true first responders. Many services and the U.S. Department of Homeland Security teach the public a simple sequence for an active attack, often summarized as run, hide, fight: get out if there is a safe way out, hide and lock or barricade the door if there is not, and, only as a last resort when life is in immediate danger, act to disrupt or stop the attacker. The Stop the Bleed program adds a fourth idea for the moments after: once it is safe, apply pressure to a bleeding wound and, if a bleeding control kit is available, pack the wound or apply a tourniquet. Some schools, malls and workplaces now keep public bleeding control kits next to their defibrillators.
For police, the public's actions shape the scene the officers enter. People who have run are outside and need to be met, identified and moved away from the building. People who are hiding behind locked doors may not open them for anyone until they are sure the person outside is a real officer. And people who have helped the wounded may be covered in blood and mistaken for victims or attackers. During the Harbor Point exercise, a role player who had applied a tourniquet to a friend was ordered to the floor by an officer who saw blood on his hands and then quickly recognized what he had done. The observers counted that as a good catch, and as a reason to brief officers that bloody hands may belong to a helper.
Medical care on other high-risk calls
Medical readiness matters on every high-risk call, not only active threats. On a high-risk vehicle stop, an occupant may be injured in a collision or by force. On a barricade, the person inside may harm themselves or come out injured. On a building search, a dog bite or a fall may need care. Good planning includes paramedics on standby for high-risk calls where injuries are possible, first aid kits carried by the officers closest to the action and a plan for who gives care. The April 10 review, covered in lesson 12, found that the arrest car at Kingsway Plaza had no first aid kit within reach, a gap that would have mattered if anyone had been hurt.
Police also have a duty of care toward people in their custody, including suspects who have been injured. Once a threat is controlled, an injured attacker or suspect must receive medical care like anyone else. Desjardins tells the students that this is both a legal duty and a mark of professionalism. 'At the end of the call, the man who caused it is a patient,' he says. 'You give him the same care you would give anyone.'
Worked problem
Minutes saved by bleeding control
A role player's card says that without a tourniquet he will die eleven minutes after being wounded. He was wounded at 08:51. A tourniquet was applied at 08:59, and the first rescue task force reached him at 09:06. What would have happened if officers had waited for the rescue task force?
Show solution
- Without a tourniquet, he dies at 08:51 plus 11 minutes, which is 09:02.
- The rescue task force reached him at 09:06, four minutes after that.
- The tourniquet at 08:59 was applied three minutes before he would have died.
Answer: If officers had waited, he would have died about four minutes before the rescue task force arrived. Officer-applied bleeding control in the first minutes is what kept him alive.
Common mistakes
MistakeParamedics should wait outside until the whole building is declared secure.
InsteadRescue task forces with police protection enter the warm zone to treat and remove the wounded.
MistakeTourniquets should only be used as a last resort.
InsteadProperly applied tourniquets save lives and are a first-line treatment for severe limb bleeding.
MistakeThe zones on an active threat are fixed at the start.
InsteadZones change as officers move and information arrives, and changes must be broadcast.
MistakeAn injured attacker is not owed medical care.
InsteadOnce the threat is controlled, police have a duty of care to every injured person in custody.
Summary and key terms
- Uncontrolled bleeding from limb wounds is a leading preventable cause of death, and can kill in minutes.
- The Hartford Consensus set the THREAT priorities and called for police and public bleeding control training.
- Officers carrying tourniquets and trained in tactical casualty care are often the first medical responders.
- Hot, warm and cold zones guide where police, rescue teams and medical services work.
- Rescue task forces of medical responders with police escorts treat and remove the wounded from the warm zone.
- Triage, casualty collection and coordinated transport get the most seriously hurt to the right hospital first.
- Hartford Consensus
- Recommendations from a 2013 expert group on improving survival from active shooter and mass casualty incidents.
- Warm zone
- An area cleared or passed through by police but not yet fully secure.
- Rescue task force
- Medical responders with protective equipment and police escort who treat and remove the wounded from the warm zone.
- Triage
- Sorting the wounded by urgency so that those who can be saved with quick care get it first.
Practice problems
Work each problem on paper first, then reveal the answer to check.
Why does bleeding control come before the arrival of paramedics?
Show answer
Severe limb bleeding can kill in minutes, faster than paramedics can reach the wounded in an insecure scene.
What does THREAT stand for?
Show answer
Threat suppression, hemorrhage control, rapid extrication, assessment by medical providers, transport.
What is a rescue task force?
Show answer
A team of paramedics or firefighters with police escort that treats and removes the wounded from the warm zone.
What medical gap did the April 10 review find?
Show answer
The arrest car had no first aid kit within reach.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.