
HSE-245 · Lesson 8 of 12 · 29 min
Bloodborne pathogens and universal precautions
Bloodborne pathogens are infectious agents carried in blood and some other body fluids that can cause disease when they enter another person's bloodstream or mucous membranes. The three that matter most at work are hepatitis B virus (HBV), hepatitis C virus (HCV) and human immunodeficiency virus (HIV). Workers in health care, dentistry, personal services, laboratories, first response, corrections, cleaning, waste handling and even teaching and office first aid can be exposed. This lesson explains the pathogens, the body fluids that carry them, how they are transmitted at work, and the core practice of treating all blood and body fluids as potentially infectious.
The three main bloodborne pathogens
Hepatitis B virus infects the liver. Many adults clear the infection, but some develop chronic infection that can lead to cirrhosis and liver cancer years later. HBV is far more infectious than HIV: it is present in very high concentrations in the blood of infected people and can survive in dried blood on surfaces for at least seven days. Before vaccination became routine for health care workers, thousands of them were infected every year in North America, and hundreds died. A safe, highly effective vaccine has been available since the 1980s.
Hepatitis C virus also infects the liver and becomes chronic in most people who are infected, often without symptoms for decades. There is no vaccine, but modern direct-acting antiviral medicines cure more than 95 percent of infections after a course of 8 to 12 weeks. Early detection after an exposure therefore matters.
Human immunodeficiency virus attacks the immune system and, untreated, leads to AIDS. Modern antiretroviral treatment lets people with HIV live long, healthy lives, and people whose viral load is suppressed by treatment do not transmit HIV sexually. After a workplace exposure, post-exposure prophylaxis (PEP), started as soon as possible and ideally within two hours, greatly reduces the chance of infection. Occupational HIV infection is now extremely rare in North America.
Other bloodborne pathogens include syphilis, malaria, viral hemorrhagic fevers such as Ebola, and others, but these are much less common workplace risks in Canada and the United States.
Which fluids carry the risk
| Higher-risk fluids and materials | Lower-risk unless visibly bloody |
|---|---|
| Blood and blood products | Saliva (except in dentistry, where it is treated as potentially infectious) |
| Semen and vaginal secretions | Urine |
| Cerebrospinal, synovial, pleural, pericardial, peritoneal and amniotic fluids | Stool and vomit |
| Any body fluid visibly contaminated with blood | Tears, sweat and nasal secretions |
| Unfixed human tissues or organs; HIV- or HBV-containing cultures in laboratories | Breast milk (except in some specific settings) |
OSHA's Bloodborne Pathogens standard calls the higher-risk fluids "other potentially infectious materials" (OPIM). It also treats any body fluid as OPIM when it is difficult or impossible to tell whether it contains blood. Fluids in the lower-risk column can still carry other infections, such as norovirus in stool and vomit.
How exposure happens at work
Transmission at work needs infected blood or fluid to reach the bloodstream or a mucous membrane. The main routes are:
- percutaneous injuries: needlesticks, cuts from scalpels, broken glass or other sharp objects contaminated with blood;
- mucous membrane exposures: splashes of blood or fluid into the eyes, nose or mouth;
- non-intact skin exposures: contact with skin that is chapped, abraded, cut or affected by dermatitis;
- bites that break the skin, in rare cases.
Intact skin is an excellent barrier, so blood on unbroken skin is not considered an exposure, although it should be washed off promptly. Hollow-bore needles that have been in a vein or artery carry the highest risk because they hold more blood than solid needles or suture needles.
The size of the risk
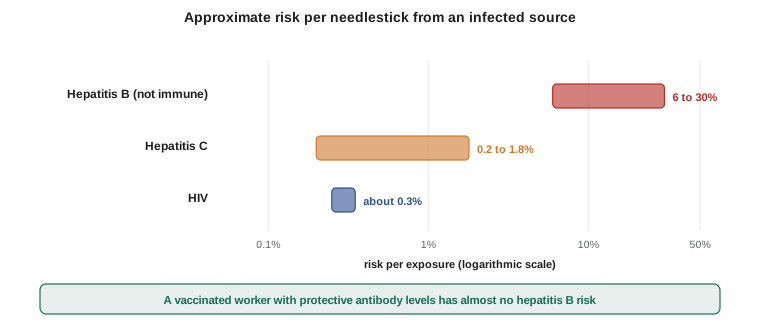
The chance of infection after a single needlestick from an infected source varies by pathogen. Estimates from older studies, often cited by public health agencies, are summarized below; actual risk depends on the amount of blood, the source's viral load, the depth of the injury and the exposed worker's immunity.
| Pathogen | Approximate risk per needlestick from an infected source | Key protection |
|---|---|---|
| Hepatitis B | 6 to 30 percent if the worker is not immune (highest when the source has high viral levels) | Vaccination; post-exposure immune globulin and vaccine for non-immune workers |
| Hepatitis C | About 1.8 percent in older studies; more recent analyses suggest about 0.2 percent | Prevent exposure; early testing and curative treatment if infected |
| HIV | About 0.3 percent; about 0.09 percent after a mucous membrane exposure | Prevent exposure; post-exposure prophylaxis started promptly |
# Expected infections from 100 needlesticks in a year, by source status (illustrative)
needlesticks = 100
share_source_positive = {"hepatitis B": 0.01, "hepatitis C": 0.02, "HIV": 0.005}
risk_per_stick = {"hepatitis B (non-immune)": 0.20, "hepatitis C": 0.018, "HIV": 0.003}
for (name, prev), (label, risk) in zip(share_source_positive.items(), risk_per_stick.items()):
    expected = needlesticks * prev * risk
    print(f"{label:<26} sources positive {prev:.1%}, risk {risk:.1%}: expected {expected:.3f} infections")
print("vaccinated responders: hepatitis B risk is close to zero")hepatitis B (non-immune) sources positive 1.0%, risk 20.0%: expected 0.200 infections hepatitis C sources positive 2.0%, risk 1.8%: expected 0.036 infections HIV sources positive 0.5%, risk 0.3%: expected 0.002 infections vaccinated responders: hepatitis B risk is close to zero
The expected numbers are small, which is the point: most individual needlesticks do not cause infection. But needlesticks are common, the consequences of infection can be lifelong, the anxiety for the worker is real, and the follow-up costs time and money. Every exposure must be prevented where possible and followed up when it happens.
Universal and standard precautions
Universal precautions, introduced by the CDC in 1987 in response to HIV, means treating all human blood and certain body fluids as if they were known to be infectious for bloodborne pathogens. It is the approach OSHA's Bloodborne Pathogens standard requires. In health care, the CDC expanded it in 1996 into standard precautions, which apply to all blood, body fluids except sweat, non-intact skin and mucous membranes, and cover contact-spread organisms as well as bloodborne ones. Outside health care, universal precautions remains the usual term. The core elements are:
- a point-of-care risk assessment before each interaction or task: what am I likely to be exposed to, and what do I need?
- hand hygiene (lesson 4);
- personal protective equipment chosen by the risk assessment: gloves for contact with blood, body fluids or contaminated items; gowns when clothing may be soiled; eye and face protection when splashes or sprays are possible;
- safe handling and disposal of sharps (lesson 9);
- respiratory etiquette;
- cleaning and disinfection of equipment and surfaces (lesson 5);
- safe handling of soiled linen and waste;
- placement of patients or clients in a way that reduces risk to others.
The exposure control plan
OSHA's Bloodborne Pathogens standard (29 CFR 1910.1030) requires every covered employer to have a written exposure control plan that is accessible to workers and reviewed at least once a year. The plan must:
- list job classifications in which all or some workers have occupational exposure, and the tasks involved;
- describe the schedule and method for implementing engineering and work practice controls, protective equipment, housekeeping, regulated waste, hepatitis B vaccination, post-exposure evaluation, training and recordkeeping;
- document the annual consideration and use of safer medical devices, with input from front-line workers who are responsible for direct patient care;
- include the procedure for evaluating exposure incidents.
Employers must also keep a sharps injury log (if they are required to keep OSHA injury records), train workers at hire and every year thereafter during working hours, provide protective equipment at no cost, and keep medical records confidentially for the duration of employment plus 30 years.
Hepatitis B vaccination and immunity
Hepatitis B vaccine is given as a series, usually three doses over six months, or two doses for one newer adjuvanted product. About 90 to 95 percent of healthy adults develop protective immunity. Because some people do not respond, health care workers and others at ongoing risk of blood exposure should have their antibody level (anti-HBs) checked one to two months after completing the series; a level of at least 10 mIU/mL indicates protection. People who do not respond receive a second series and are retested; those who still do not respond are counselled about their status and need prompt immune globulin after any exposure. Once a person has shown a protective response, booster doses are not routinely recommended for healthy workers, because immune memory persists even when antibody levels later fall.
The Bloodborne Pathogens standard requires employers to make the hepatitis B vaccine series available at no cost, at a reasonable time and place, within 10 working days of initial assignment to a job with occupational exposure, unless the worker has already been vaccinated, is immune or has a medical reason not to receive it. Workers who decline must sign the declination statement in Appendix A of the standard, and the employer must provide the vaccine if they later change their mind.
# Hepatitis B vaccine response and testing in a group of 200 new health care staff (illustrative)
staff = 200
respond_first_series = 0.92
respond_second_series = 0.60     # share of first-series non-responders who respond to a second series
nonresp1 = staff * (1 - respond_first_series)
resp2 = nonresp1 * respond_second_series
nonresp_final = nonresp1 - resp2
print(f"protected after first series: {staff * respond_first_series:.0f}")
print(f"non-responders retested after second series: {nonresp1:.0f}, of whom {resp2:.0f} respond")
print(f"persistent non-responders needing advice and prompt post-exposure care: {nonresp_final:.0f}")protected after first series: 184 non-responders retested after second series: 16, of whom 10 respond persistent non-responders needing advice and prompt post-exposure care: 6
Engineering and work practice controls
Most bloodborne exposures can be prevented by controls that do not depend on perfect behavior. The most important are safety-engineered sharps, such as retractable needles, shielded needles, needleless connectors for intravenous lines and blunt suture needles where suitable; puncture-resistant sharps containers placed close to where sharps are used; and work practices such as never recapping used needles by hand, not passing sharps hand to hand in procedures (use a neutral zone instead), and disposing of sharps immediately after use. Lesson 9 covers sharps in detail.
Other work practices include not eating, drinking, applying cosmetics or handling contact lenses where exposure is possible; not storing food in refrigerators with blood or specimens; minimizing splashing and spraying; using mechanical pipetting in laboratories; and placing specimens in leak-proof containers for transport.
Worked problem
Deciding whether an incident is an exposure
During first aid on a nosebleed, blood gets on a teacher's forearm. The skin is intact. Later the same day a custodian picks up a bloody tissue with a bare hand that has a small cut. Which, if either, is an exposure?
Show solution
- Intact skin is an effective barrier; blood on the teacher's intact forearm is not considered an exposure. The teacher should wash it off with soap and water.
- The custodian's hand has a cut, so blood may have contacted non-intact skin; this counts as a potential exposure.
- The custodian should wash the area with soap and water, report it immediately and be assessed for post-exposure follow-up (lesson 9).
- The workplace should review why a bloody tissue was handled bare-handed and provide gloves and training.
Answer: The teacher's contact is not an exposure; the custodian's contact with a cut is, and needs immediate reporting and assessment.
Worked problem
Building routine practices into a dental hygiene appointment
A dental hygienist is about to do a scaling procedure. Apply a point-of-care risk assessment.
Show solution
- Scaling produces spatter and aerosols containing saliva and blood, and uses sharp instruments.
- Hand hygiene before gloves, and gloves for contact with the mouth.
- Eye protection and a mask (or a respirator if the risk assessment calls for one) because spatter is expected, plus a protective gown.
- Use high-volume evacuation to reduce aerosols, handle sharp instruments carefully and place them in a cassette or tray for reprocessing as critical items.
- Clean and disinfect the operatory surfaces between patients.
Answer: Treat saliva and blood as potentially infectious and combine hand hygiene, gloves, eye and face protection, gowns, sharps care, aerosol reduction and cleaning.
Common mistakes
MistakeUsing routine precautions only for patients known to have an infection.
InsteadTreat all blood and body fluids as potentially infectious, every time.
MistakeAssuming hepatitis C and HIV are the biggest needlestick risks.
InsteadHepatitis B is far more transmissible for non-immune workers; vaccination is the key protection.
MistakeSkipping post-vaccination antibody testing for workers at ongoing risk.
InsteadTest anti-HBs one to two months after the series to identify non-responders.
MistakeRecapping a used needle by hand.
InsteadDispose of it immediately in a sharps container, or use a one-handed technique or device where recapping is unavoidable.
MistakeTreating blood on intact skin as a serious exposure while ignoring blood on a cut.
InsteadIntact skin is a barrier; non-intact skin, mucous membranes and sharps injuries are exposures.
Summary and key terms
- Hepatitis B, hepatitis C and HIV are the main bloodborne pathogens at work.
- Blood and certain body fluids carry the risk; fluids visibly contaminated with blood count too.
- Exposure needs blood to reach the bloodstream through sharps injuries, mucous membranes or non-intact skin.
- Per-needlestick risk is highest for hepatitis B in non-immune workers, lower for hepatitis C and lowest for HIV.
- Universal and standard precautions treat all blood and certain body fluids as potentially infectious.
- OSHA requires a written exposure control plan, reviewed yearly, with safer device evaluation and records.
- Hepatitis B vaccine protects most adults; workers at ongoing risk should have their antibody level checked after the series.
- Bloodborne pathogen
- An infectious agent in blood that can cause disease, such as HBV, HCV or HIV.
- Other potentially infectious materials (OPIM)
- Body fluids and tissues treated like blood for bloodborne pathogen purposes.
- Percutaneous injury
- An injury that breaks the skin, such as a needlestick or cut.
- Mucous membrane
- The moist lining of the eyes, nose, mouth and other body openings.
- Routine practices
- The Canadian term for infection prevention practices used with everyone at all times.
- Universal precautions
- Treating all human blood and certain body fluids as if known to be infectious.
- Standard precautions
- The CDC's expanded set of practices used with all patients in health care.
- Point-of-care risk assessment
- A quick assessment before each task of the likely exposure and the controls needed.
- Anti-HBs
- Antibody to hepatitis B surface antigen; 10 mIU/mL or more indicates protection.
- Post-exposure prophylaxis (PEP)
- Medicine given after an exposure to prevent infection, such as antiretrovirals for HIV.
Practice problems
Work each problem on paper first, then reveal the answer to check.
Name the three main bloodborne pathogens of concern at work.
Show answer
Hepatitis B virus, hepatitis C virus and HIV.
Which is most transmissible by needlestick for a non-immune worker?
Show answer
Hepatitis B, with a risk of about 6 to 30 percent from an infected source.
Is urine without visible blood considered high risk for bloodborne pathogens?
Show answer
No, but routine practices still apply because it can carry other infections.
What makes hollow-bore needles higher risk than solid needles?
Show answer
They can hold more blood.
What are the core elements of routine practices?
Show answer
Point-of-care risk assessment, hand hygiene, PPE chosen by risk, sharps safety, respiratory etiquette, cleaning, safe linen and waste handling, and patient placement.
When should anti-HBs be tested after hepatitis B vaccination?
Show answer
One to two months after completing the series, for workers at ongoing risk.
What anti-HBs level indicates protection?
Show answer
At least 10 mIU/mL.
Why is early testing after a hepatitis C exposure important?
Show answer
Infection can be cured with antiviral medicines, so early detection allows timely treatment.
Name two engineering controls for bloodborne exposures.
Show answer
Any two of safety-engineered sharps, needleless connectors, blunt suture needles and puncture-resistant sharps containers.
How often must an OSHA exposure control plan be reviewed?
Show answer
At least once a year.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.