
BIOL-450 · Lesson 7 of 12 · 24 min
The tumor microenvironment and angiogenesis
A tumor is not a ball of identical cancer cells. It is an organ-like tissue in which cancer cells live among blood vessels, fibroblasts, immune cells, nerves and an extracellular matrix that they both build and remodel. This tumor microenvironment shapes growth, invasion, response to treatment and immune evasion. Stephen Paget's seed and soil idea, proposed in 1889 for metastasis, applies to primary tumors too: the cancer cell is the seed, but the soil decides whether it thrives. This lesson covers the components of the microenvironment, the biology of tumor blood vessels and hypoxia, and the drugs that target them. Immune cells in the microenvironment are covered in depth in BIOL-380 and are only summarized here.
Components of the microenvironment
Cancer-associated fibroblasts (CAFs) are the most abundant stromal cells in many carcinomas. Activated by signals such as TGF-β from cancer cells, they deposit and stiffen collagen, secrete growth factors and cytokines, and remodel the matrix. In pancreatic adenocarcinoma, a dense fibrotic stroma, called desmoplasia, can make up most of the tumor mass and impede drug delivery. CAFs are heterogeneous: some subtypes promote tumor growth, while others restrain it, which helps explain why early attempts to deplete stroma in mouse models of pancreatic cancer sometimes made tumors more aggressive.
The extracellular matrix, a network of collagens, fibronectin, laminins and proteoglycans, is more than scaffolding. Its stiffness signals through integrins to promote proliferation and invasion; its fragments, released by matrix metalloproteinases, carry their own signals; and it stores growth factors such as VEGF and TGF-β that are released when the matrix is cleaved. Immune cells are abundant in many tumors: T cells, natural killer cells, macrophages, neutrophils, dendritic cells and myeloid-derived suppressor cells. Tumor-associated macrophages often adopt a state that promotes angiogenesis, matrix remodeling and immune suppression. Whether immune cells attack the tumor or are co-opted to help it is a central question of tumor immunology, covered in BIOL-380. Nerves grow into some tumors and can promote their growth, an emerging area sometimes called cancer neuroscience.
Why tumors need blood vessels
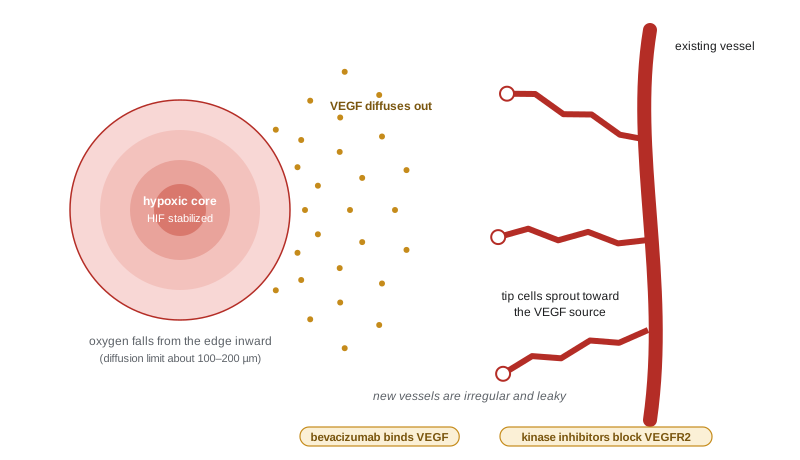
Oxygen diffuses only a limited distance from a capillary before cells consume it. In well-perfused tissue every cell is within about 100 to 200 micrometers of a capillary. A cluster of tumor cells can therefore stay fully oxygenated only up to about half a millimeter across; beyond that its center becomes hypoxic and then dies, and growth stalls at around a millimeter or two, with a living rim around a dead core. Judah Folkman proposed in 1971 that tumor growth beyond this size depends on angiogenesis, the sprouting of new blood vessels from existing ones, and that blocking angiogenesis could hold tumors in a dormant, harmless state. His idea, initially greeted with doubt, launched a field.
# How far does oxygen reach from a capillary? Krogh-type estimate in a tumour cord (illustrative values).
import numpy as np
D = 2.0e-5         # O2 diffusion coefficient in tissue, cm^2/s
C0 = 1.3e-7        # O2 concentration at the vessel wall, mol/cm^3 (about 100 mmHg)
for name, M in [('resting tissue', 1.0e-8), ('tumour cord', 3.0e-8)]:   # consumption, mol/(cm^3 s)
    # planar approximation: C(x) = C0 - M x (2L - x)/(2D) reaches zero at L = sqrt(2 D C0 / M)
    L = np.sqrt(2 * D * C0 / M)
    print(f"{name:15s}: oxygen falls to zero about {L * 1e4:.0f} micrometres from the vessel")
# growth limit of an avascular spheroid: necrotic core appears once radius exceeds roughly the diffusion limit
r_lim_um = np.sqrt(6 * D * C0 / 3.0e-8) * 1e4      # spherical case: R = sqrt(6 D C0 / M)
print(f"avascular spheroid: necrotic core expected once radius exceeds about {r_lim_um:.0f} micrometres")
print(f"so the largest well-oxygenated avascular nodule is about {2 * r_lim_um / 1000:.1f} mm across")resting tissue : oxygen falls to zero about 228 micrometers from the vessel tumor cord : oxygen falls to zero about 132 micrometers from the vessel avascular spheroid: necrotic core expected once radius exceeds about 228 micrometers so the largest well-oxygenated avascular nodule is about 0.5 mm across
Simple diffusion-consumption models, first applied by August Krogh to muscle a century ago, give distances on the order of 100 to 200 micrometers, matching the thickness of viable tumor cords seen around vessels in histology sections and the size at which cultured tumor spheroids develop necrotic cores. The numbers are illustrative, because consumption varies widely between cell types, but they explain why a tumor must recruit blood vessels to grow beyond a small nodule.
The angiogenic switch
Normal adult vasculature is mostly quiescent, held in balance by pro- and anti-angiogenic signals. Tumors tip the balance, a change Douglas Hanahan and Folkman called the angiogenic switch. The best studied pro-angiogenic factor is vascular endothelial growth factor A (VEGF-A), discovered by Napoleone Ferrara and others. VEGF binds VEGF receptor 2 on endothelial cells, stimulating them to proliferate, migrate and form new sprouts, and it makes vessels leaky. Hypoxia is a powerful trigger. Under normal oxygen, prolyl hydroxylases mark the α subunit of hypoxia-inducible factor (HIF) with hydroxyl groups, the von Hippel–Lindau protein (VHL) recognizes them, and HIF-α is degraded. Under hypoxia the hydroxylases stall, HIF-α accumulates, partners with HIF-1β and switches on genes for VEGF, glycolysis (lesson 6), erythropoietin and survival. William Kaelin, Peter Ratcliffe and Gregg Semenza received the 2019 Nobel Prize in Physiology or Medicine for discovering how cells sense and adapt to oxygen.
Clear cell renal cell carcinoma shows the pathway in action. Most of these tumors lose VHL, through inherited von Hippel–Lindau disease or somatic mutation and deletion, so HIF-2α is stabilized regardless of oxygen and VEGF is produced constantly. These are among the most vascular of all tumors, and VEGF pathway inhibitors such as sunitinib and axitinib became standard treatments. Belzutifan, an inhibitor of HIF-2α, was approved in the United States in 2021 for tumors associated with von Hippel–Lindau disease and later for advanced renal cell carcinoma (approval status as of 2026; check current labels).
Abnormal tumor vessels
Tumor vessels are not like normal ones. They are tortuous, dilated and disorganized, with uneven diameters, dead ends and blood flowing in changing directions. Their walls are leaky, with gaps between endothelial cells and poor coverage by pericytes, so plasma leaks into the tumor and raises interstitial fluid pressure. Some regions are well perfused while others are hypoxic and acidic, and hypoxia fluctuates as vessels open and close. These abnormalities matter clinically. High interstitial pressure and poor perfusion limit the delivery of drugs, and hypoxic cells resist radiation, which kills cells largely by generating oxygen-dependent DNA damage, and resist many chemotherapy drugs. Hypoxia also selects for more aggressive, invasive cells and suppresses immune responses.
Tumors do not rely only on sprouting angiogenesis. They can co-opt existing vessels, growing along them as glioblastoma cells and some lung and liver metastases do; recruit circulating endothelial progenitors; and, in a controversial process called vascular mimicry, form vessel-like channels lined by tumor cells. These alternatives help explain why blocking VEGF alone rarely starves a tumor completely.
Anti-angiogenic therapy
Bevacizumab, an antibody that binds VEGF-A, was approved by the FDA in 2004 for metastatic colorectal cancer in combination with chemotherapy, after a trial showed improved survival. Small-molecule kinase inhibitors of VEGF receptors, including sunitinib, sorafenib, pazopanib and axitinib, followed, especially for renal cell carcinoma and liver cancer. Results have been more modest than Folkman hoped. In many cancers, bevacizumab added months of progression-free survival but little or no overall survival, and its approval for metastatic breast cancer in the United States was withdrawn in 2011. Tumors adapt by switching to other angiogenic factors, such as fibroblast growth factors and angiopoietins, by co-opting vessels, or by becoming more invasive under hypoxia.
Rakesh Jain proposed a different interpretation: carefully dosed anti-angiogenic drugs can normalize tumor vessels for a time, pruning abnormal ones and improving perfusion and oxygenation, which can make chemotherapy, radiation and immunotherapy work better. Combinations of VEGF blockade with immune checkpoint inhibitors, such as atezolizumab with bevacizumab for advanced liver cancer, reflect this idea and are now standard in some settings.
Measuring and targeting hypoxia
Because hypoxia predicts poor response to radiation and surgery alone, several ways of measuring it have been developed. Oxygen electrodes inserted into tumors, used in pioneering studies of cervical and head and neck cancers in the 1990s, showed that patients with more hypoxic tumors had worse outcomes. Nitroimidazole compounds such as pimonidazole are reduced and trapped only in hypoxic cells and can be detected in biopsies, and a radiolabelled relative, 18F-fluoromisonidazole (FMISO), images hypoxia by PET. Attempts to exploit hypoxia therapeutically include hypoxia-activated prodrugs, which release a toxic agent only in low oxygen; evofosfamide, the most advanced, failed in phase 3 trials in pancreatic cancer and sarcoma. Radiation oncologists have more often addressed hypoxia indirectly, by dividing doses into fractions so that hypoxic regions reoxygenate between treatments, and by combining radiation with chemotherapy.
Inflammation and the tumor
Rudolf Virchow noted in the nineteenth century that tumors often arise at sites of chronic inflammation. Tumor-promoting inflammation is now an enabling characteristic of cancer. Chronic infection with hepatitis viruses or Helicobacter pylori, inflammatory bowel disease, and chronic exposure to irritants such as asbestos create a tissue environment rich in reactive oxygen species, which damage DNA, and in cytokines such as interleukin-6 and TNF, which activate NF-κB and STAT3 signaling in epithelial cells to promote survival and proliferation. Long-term use of aspirin is associated with a lower risk of colorectal cancer, consistent with a role for inflammation, though aspirin is not recommended for cancer prevention in the general population because of bleeding risk.
| Component | Main roles in the tumor | Therapeutic angle |
|---|---|---|
| Cancer-associated fibroblasts | Matrix deposition, growth factors, drug barrier; some subtypes restrain tumors | Stromal targeting (cautious, trials) |
| Extracellular matrix | Stiffness signaling, growth factor reservoir, invasion routes | Protease and integrin targeting (mostly research) |
| Blood vessels | Oxygen and nutrient supply, leaky and abnormal | Bevacizumab, VEGF receptor kinase inhibitors, HIF-2α inhibitor |
| Macrophages and myeloid cells | Angiogenesis, matrix remodeling, immune suppression | Myeloid reprogramming (trials) |
| T and NK cells | Tumor killing, often suppressed | Checkpoint inhibitors, cell therapy (BIOL-380) |
| Nerves | Growth signals, pain, spread along nerves | Emerging research area |
For Maya, the microenvironment matters in two ways. Her tumor's hypoxic regions, inferred from variable FDG uptake, may resist radiation, and her treatment plan combines chemotherapy and radiation, then immunotherapy, an approach in which the microenvironment's immune cells are the target. Her oncologist also considered whether a regimen including bevacizumab might suit her later, a choice limited by her tumor's location near large central vessels, where bleeding is a known risk of VEGF inhibitors.
Worked problem
Estimating an oxygen diffusion limit
In a planar tissue model, oxygen at a vessel wall is 1.3 x 10 to the power -7 mol/cm3, the diffusion coefficient is 2 x 10 to the power -5 cm2/s and cells consume oxygen at 2 x 10 to the power -8 mol/(cm3 s). Using L = square root of (2 D C0 / M), estimate how far oxygen reaches.
Show solution
- 2 D C0 = 2 x 2 x 10 to the power -5 x 1.3 x 10 to the power -7 = 5.2 x 10 to the power -12.
- Divide by M: 5.2 x 10 to the power -12 / 2 x 10 to the power -8 = 2.6 x 10 to the power -4 cm2.
- Square root: L = 1.6 x 10 to the power -2 cm.
- Convert: 0.016 cm = 160 micrometers.
Answer: About 160 micrometers, consistent with the thickness of viable tumor cords around vessels.
Common mistakes
MistakePicturing a tumor as a uniform mass of cancer cells.
InsteadTumors contain fibroblasts, vessels, immune cells, nerves and matrix that shape their behavior.
MistakeExpecting anti-angiogenic drugs to starve tumors completely.
InsteadTumors adapt with other factors and vessel co-option; benefits are often modest and may come from vessel normalization.
MistakeTreating hypoxia as a minor detail.
InsteadHypoxia drives HIF signaling, resistance to radiation and drugs, invasion and immune suppression.
MistakeAssuming all fibroblasts in tumors help cancer.
InsteadCAFs are heterogeneous; some restrain tumor growth.
MistakeConcluding that aspirin should be taken by everyone to prevent cancer.
InsteadAssociations with lower colorectal risk must be weighed against bleeding risk; it is not generally recommended for prevention.
Summary and key terms
- The tumor microenvironment includes fibroblasts, matrix, vessels, immune cells and nerves that shape tumor behavior.
- Oxygen penetrates only about 100 to 200 micrometers from capillaries, so tumors need new vessels to grow beyond small nodules.
- Hypoxia stabilizes HIF, which induces VEGF; VHL loss in clear cell renal cancer makes this constitutive.
- Tumor vessels are abnormal and leaky, causing hypoxia, high interstitial pressure and poor drug delivery.
- Anti-angiogenic drugs give real but often modest benefits; resistance and vessel normalization explain much of their behavior.
- Chronic inflammation promotes cancer through DNA damage and pro-survival signaling.
- tumor microenvironment
- The non-cancer cells, matrix and signals surrounding and within a tumor.
- cancer-associated fibroblast
- An activated fibroblast in a tumor that remodels matrix and secretes signals.
- desmoplasia
- Dense fibrous stroma surrounding a tumor.
- angiogenesis
- Formation of new blood vessels from existing ones.
- angiogenic switch
- The shift in balance toward pro-angiogenic signals that lets a tumor recruit vessels.
- VEGF
- Vascular endothelial growth factor, the main stimulator of angiogenesis.
- HIF
- Hypoxia-inducible factor, a transcription factor stabilized at low oxygen.
- VHL
- The von Hippel–Lindau tumor suppressor, which targets HIF-α for degradation when oxygen is present.
- vessel normalization
- Temporary restoration of more normal tumor vessel structure and function by anti-angiogenic therapy.
- interstitial fluid pressure
- Pressure of fluid in tissue spaces, elevated in tumors by leaky vessels.
Practice problems
Work each problem on paper first, then reveal the answer to check.
Why does an avascular tumor stall at about 1 to 2 mm?
Show answer
Oxygen and nutrients diffuse only about 100 to 200 micrometers before being consumed, so the core becomes hypoxic and dies.
How does hypoxia increase VEGF production?
Show answer
Prolyl hydroxylases stall, HIF-α escapes VHL-mediated degradation, and HIF induces VEGF.
Why are clear cell renal cancers highly vascular?
Show answer
VHL loss stabilizes HIF-2α and drives constant VEGF expression.
Give two reasons hypoxic tumor cells resist radiation.
Show answer
Radiation damage depends on oxygen; hypoxic cells are also often non-dividing and selected for survival.
What is vessel co-option?
Show answer
Tumor cells growing along pre-existing vessels instead of inducing new ones.
What did Jain propose about anti-angiogenic drugs?
Show answer
They can transiently normalize tumor vessels and improve delivery of other treatments.
Name a drug that binds VEGF-A directly.
Show answer
Bevacizumab.
How does chronic inflammation promote cancer?
Show answer
Reactive oxygen species damage DNA, and cytokines activate pro-survival signaling such as NF-κB and STAT3.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.