
HSE-392 · Lesson 10 of 12 · 25 min
Post-exposure follow-up and reporting
▶ Video coming soon A video version of this lesson is on the way.
Lesson 9 covered the first minutes and hours after an exposure: first aid, an immediate report and a prompt assessment. This lesson covers what comes next, over the following days and months. That means the treatment decisions for each of the three viruses, the schedule of follow-up blood tests, what the exposed worker should do while waiting for results, how the hospital records and reports the exposure, and how it learns from each one so the next worker is not hurt the same way.
Most exposures end well. In the great majority, the source patient tests negative for all three viruses, or the worker is already immune to hepatitis B, and follow-up stops early. Even when the source is infected, the chance of infection from a single exposure is small, as Lesson 1 showed, and the steps in this lesson make it smaller still. But follow-up only works if it is finished, and the most common failure is not a medical one: it is a worker who misses the later blood tests because they feel fine and life gets busy.
Three viruses, three different plans
The follow-up depends on which virus is in question, because the tools available for each are different. Hepatitis B can be prevented after an exposure in a worker who is not immune. HIV infection can usually be prevented with drugs if they are started quickly. Hepatitis C has no preventive treatment, so follow-up is about finding an infection early, when it can be cured.
| Hepatitis B | Hepatitis C | HIV | |
|---|---|---|---|
| If the source is negative | No treatment; follow-up can stop | No further testing needed | No PEP; stop it if it was started |
| If the worker is immune | No treatment needed | Not applicable: no vaccine | Not applicable: no vaccine |
| Treatment after exposure | Vaccine and, if not immune, hepatitis B immune globulin | None to prevent infection | Post-exposure prophylaxis for 28 days |
| Best timing | Within 24 hours; usually not after 7 days | Not applicable | Within hours; generally not after 72 hours |
| Follow-up testing | Only for workers who were not immune | Testing over about 6 months | Testing to about 4 to 6 months |
| If infection occurs | Specialist care; most adults clear it | Antiviral drugs cure most people | Lifelong treatment; normal life expectancy |
Hepatitis B: protecting the worker who is not immune
For hepatitis B, the deciding question is the worker's own immune status, which is why Lesson 8 put so much weight on testing antibodies after the vaccine series. A worker with a documented protective anti-HBs result at any time in the past needs nothing further, even if the source has hepatitis B. Their immune memory protects them.
For a worker who is not known to be immune, the plan depends on the source:
- Source positive for hepatitis B surface antigen, or unknown and high risk: the worker receives hepatitis B immune globulin (HBIG) and starts or restarts the vaccine, ideally within 24 hours. A worker who is a known non-responder after two full series receives two doses of HBIG a month apart.
- Source negative: no HBIG. A worker who is unvaccinated or partly vaccinated starts or completes the vaccine series, because the next exposure might not be so lucky.
- Vaccinated but never tested: the worker is tested for anti-HBs right away. If the result is protective, nothing more is needed. If not, they are treated as not immune while the source result is awaited.
HBIG gives ready-made antibodies that protect for a few months while the vaccine builds the worker's own. Workers who receive HBIG after an exposure to a positive source have blood tests over the following months to confirm that they were not infected and that the vaccine has now worked.
Hepatitis C: testing and early treatment
There is no vaccine and no preventive treatment for hepatitis C. Follow-up is about knowing quickly whether infection happened. Current guidance, which the Northbridge protocol follows, looks like this:
- The source patient, with consent, is tested for hepatitis C antibody and, if that is positive, for HCV RNA, which shows the virus is actually present.
- The worker has a baseline antibody test as soon as possible after the exposure, ideally within 48 hours, to show their status before any infection.
- If the source has the virus or their status cannot be found, the worker is tested for HCV RNA at about 3 to 6 weeks, which finds a new infection much earlier than antibody testing alone.
- A final antibody test, and an RNA test if it is positive, is done at about 4 to 6 months.
If a worker does become infected, they are referred to a specialist promptly. Modern direct-acting antiviral drugs, taken for 8 to 12 weeks, cure more than 95 in 100 people treated. That is a very different outcome from twenty years ago, and it is a strong reason not to skip the later tests: an infection found early is treated early.
HIV: post-exposure prophylaxis
HIV post-exposure prophylaxis, often called PEP, is a 28-day course of antiretroviral drugs that greatly reduces the chance that HIV establishes itself after an exposure. The decision to start it depends on the type of exposure and what is known about the source.
- A clear exposure to blood from a source known to have HIV: PEP is recommended, started as soon as possible.
- A source whose status is unknown: the decision is based on the circumstances and on how likely the source is to have HIV. PEP is often started right away and stopped if the source tests negative.
- A source with HIV whose virus is fully suppressed by treatment: PEP is still usually offered after a needlestick, because the level of virus in the blood at that moment is not known for certain, but the risk is very low. An expert, such as the hospital's infectious disease physician or a national clinician consultation service, helps with the decision.
- An exposure to a fluid that does not carry HIV, such as urine without visible blood, or to intact skin: PEP is not recommended.
Current regimens are usually three drugs, often taken as one or two pills a day, and are much easier to tolerate than older ones. Common side effects are nausea, tiredness and headache, which usually ease after the first week. The choice of drugs follows current US Public Health Service and CDC guidance and takes into account the worker's other medicines, kidney function and the possibility of pregnancy. Under the Bloodborne Pathogens standard, the evaluation, the drugs and the follow-up are provided to the employee at no cost, and Northbridge keeps a starter supply in the emergency department.
Taking every dose matters. Workers who stop early because of side effects or because they feel the risk was small lose much of the protection. Employee Health and Safety sees each worker on PEP within about 72 hours of starting, to review the source results, check side effects and decide whether to continue, and keeps in touch through the 28 days.
HIV testing of the worker is done at baseline, at about 6 weeks and at about 4 months when the newer combined antigen and antibody tests are used. Some protocols add a later test, for example when the worker became infected with hepatitis C from the same exposure, because that can delay HIV antibodies.
The follow-up schedule
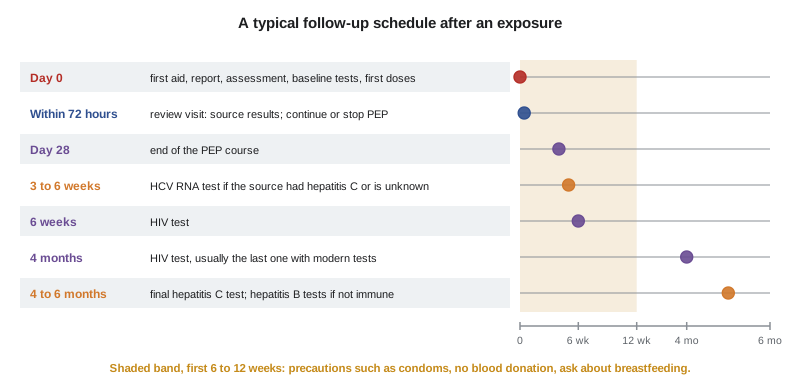
The dates depend on the exposure date, and keeping track of them is a job Employee Health and Safety takes on, not something left to the worker to remember. At Northbridge, the nurse sets the dates on the day of the assessment, gives the worker a printed card, books the first two visits and sends reminders before each one. Joanne uses a short script to produce the schedule for the card.
from datetime import date, timedelta

def schedule(exposed, source):
    """Follow-up visits after an exposure; source is a set of positive or unknown results."""
    plan = [(0, "baseline blood tests (HBV, HCV, HIV) and first aid record")]
    if "HIV" in source:
        plan += [(3, "review visit: source results, PEP side effects"),
                 (28, "last day of PEP; adherence check"),
                 (42, "HIV test (6 weeks)"),
                 (120, "HIV test (4 months), usually the last")]
    if "HCV" in source:
        plan += [(28, "HCV RNA test (3 to 6 weeks)"),
                 (150, "final HCV antibody test (4 to 6 months)")]
    if "HBV" in source:
        plan += [(1, "HBIG and vaccine dose if not immune"),
                 (180, "hepatitis B tests if the worker was not immune")]
    return sorted((exposed + timedelta(days=d), task) for d, task in plan)

for day, task in schedule(date(2026, 3, 4), {"HIV", "HCV"}):
print(day.isoformat(), " ", task)2026-03-04 baseline blood tests (HBV, HCV, HIV) and first aid record 2026-03-07 review visit: source results, PEP side effects 2026-04-01 HCV RNA test (3 to 6 weeks) 2026-04-01 last day of PEP; adherence check 2026-04-15 HIV test (6 weeks) 2026-07-02 HIV test (4 months), usually the last 2026-08-01 final HCV antibody test (4 to 6 months)
The example is for a source whose HIV and hepatitis C status could not be determined, the situation in which follow-up is longest. If the source's tests come back negative a day later, most of the schedule is canceled, and the nurse tells the worker so in person.
Precautions while waiting
Until the follow-up shows no infection, the exposed worker is asked to take some simple precautions, mostly in the first 6 to 12 weeks when the risk of passing on an undetected infection would be highest:
- Use condoms or other barriers during sex.
- Do not donate blood, plasma, organs, tissue or semen.
- Discuss breastfeeding with the clinician, especially after an exposure to a source with HIV.
- Avoid sharing razors or toothbrushes.
- Report any illness such as fever, rash, swollen glands or a flu-like illness, which can be a sign of early HIV infection, or yellowing of the skin or eyes, which can be a sign of hepatitis.
There is no need for the worker to change how they work with patients. A worker who follows standard precautions does not put patients at risk during the follow-up period, and they can keep working normally. If a worker were ever found to be infected, the questions about their work would be handled confidentially by Employee Health and Safety and expert advisers, following national guidance, which in most cases allows them to continue in their job.
Confidentiality
Everything about an exposure is personal health information: the worker's test results, their immune status, the source patient's results and the treatment given. Under the Bloodborne Pathogens standard, the employer keeps a confidential medical record for each employee with occupational exposure, separate from the personnel file, for the length of employment plus 30 years, and does not disclose it without the employee's written consent except as the law requires. The healthcare professional's written opinion to the employer, provided within 15 days of the evaluation, is limited to whether hepatitis B vaccine was indicated and received, that the employee was told the results and about any conditions needing further care; all other findings stay confidential. Managers learn only what they need to arrange cover and fix the hazard.
Reporting the exposure
Reporting has two purposes. The first is to protect the worker: a properly recorded exposure is the basis for any compensation claim, and it matters a great deal if the worker were ever to become infected years later and need to show that the infection came from work. The second is prevention: each report is information about a device, a task or a place that hurt someone.
In Minnesota, the steps are:
- Internal report: the worker completes the hospital's incident report the same day, with the help of the charge nurse if needed. The report records what happened and the device involved, without the source patient's name.
- Sharps injury log: a needlestick or cut from a contaminated sharp is entered in the sharps injury log within 7 calendar days, with the type and brand of device, the work area and how it happened, without the employee's name.
- OSHA 300 log: a needlestick or cut from a sharp contaminated with another person's blood or other potentially infectious material is recordable, and it is entered as a privacy case, so the employee's name does not appear. A splash with no wound is recorded if it leads to a diagnosed infection or to treatment beyond first aid, and an entry is updated if the worker later seroconverts.
- Workers' compensation: the hospital reports the exposure to its insurer. In Minnesota, a First Report of Injury is required within 10 days when an injury causes 3 or more days of lost time, and Northbridge files it for every exposure that leads to PEP, so the record exists if it is ever needed.
Workers sometimes worry that reporting will count against them or their unit. At Northbridge, the policy says plainly that no one is disciplined for reporting an exposure, and Sarah MacLeod reminds new staff on 4 West that the only exposure she is unhappy about is one nobody told her about.
Learning from each exposure
Every exposure report triggers a short review. The point is not to find someone to blame but to understand why the sharp ended up where it did, and what would stop it happening again. Joanne's team uses a few standard questions:
- What device was involved, and did it have a safety feature? If it did, was the feature activated, and if not, why not?
- At what point did the injury happen: during use, after use before disposal, or during or after disposal?
- Was a sharps container within reach, and was it below the fill line?
- Was the worker trained on this device? Was the patient restless, and was help available?
- Has the same thing happened before on this unit or with this device?
The answers go to the safety committee, which tracks patterns across the year. In HSE-390, sharps and splashes accounted for 19 of Northbridge's 72 claims. When Joanne reviewed those cases together, three patterns stood out: injuries during IV starts on restless patients in the emergency department, injuries when a safety feature on one model of blood collection set was activated late, and sharps found in the laundry. Each led to a specific fix: a standing rule to get a second person for IV starts on agitated patients, retraining and a device change for the blood collection sets, and the point-of-use disposal campaign described in Lesson 5.
Worked problem
Daniel's follow-up
Daniel Okafor cuts his gloved finger on a broken blood tube while clearing a jam in an analyzer. The tube's label shows the patient, who agrees to testing. The source tests positive for hepatitis C antibody and HCV RNA and negative for HIV and hepatitis B. Daniel had a protective anti-HBs result after his vaccine series eight years ago. What follow-up does he need?
Show solution
- Hepatitis B: none. His documented protective result means he is immune, whatever the source's status.
- HIV: none. The source is negative, so PEP is not needed and HIV follow-up stops after the baseline test.
- Hepatitis C: baseline antibody test within 48 hours, an HCV RNA test at about 3 to 6 weeks, and a final antibody test at about 4 to 6 months. If any test shows infection, he is referred for treatment right away.
- Reporting and review: the exposure is reported internally and to the compensation system, and the lab reviews why a broken tube had to be cleared by hand, which leads to a new rule to use forceps and a puncture-resistant tray for analyzer jams.
Answer: Hepatitis C testing over about 6 months, no PEP and no hepatitis B treatment, plus reporting and a review of how analyzer jams are cleared.
Common mistakes
MistakeSkipping the later blood tests because you feel fine.
InsteadFinish every follow-up test; early infections usually have no symptoms.
MistakeStopping PEP after a few days because of nausea.
InsteadTell occupational health; side effects can usually be managed, and the full 28 days give the protection.
MistakeTelling the unit about the source patient's results.
InsteadKeep all results confidential; managers need only what is required to fix the hazard.
MistakeTreating an exposure report as a mark against the worker.
InsteadUse each report to find and fix the cause; never discipline for reporting.
MistakeAssuming a vaccinated worker is immune without a test result.
InsteadCheck for a documented protective antibody result, or test right away.
Summary and key terms
- Follow-up depends on the virus: prevention for hepatitis B and HIV, early detection and cure for hepatitis C.
- A worker with a documented protective anti-HBs result needs no hepatitis B treatment after any exposure.
- Non-immune workers exposed to a positive or high-risk source get HBIG and vaccine, ideally within 24 hours.
- HIV PEP is a 28-day course started as soon as possible, generally not after 72 hours, with a review within about 72 hours.
- Hepatitis C follow-up uses an RNA test at 3 to 6 weeks and a final test at 4 to 6 months; cure rates are very high.
- Precautions such as condoms and not donating blood apply while follow-up is under way.
- Sharps injuries go in the sharps injury log within 7 days and on the OSHA 300 log as privacy cases.
- Each exposure is reviewed to find and fix the cause, without blame.
- Seroconversion
- The appearance of antibodies, or of the virus itself, in the blood, showing that infection has occurred.
- HCV RNA test
- A test that detects the genetic material of the hepatitis C virus, showing current infection.
- Direct-acting antivirals
- Modern drugs that cure most people with hepatitis C in 8 to 12 weeks.
- Privacy case
- An entry on an injury log in which the worker's name is left out to protect their privacy.
- Written opinion
- The healthcare professional's short report to the employer after an exposure evaluation, limited to what the employer needs to know.
Practice problems
Work each problem on paper first, then reveal the answer to check.
A worker with a documented protective anti-HBs result is exposed to a source with hepatitis B. What treatment do they need?
Show answer
None for hepatitis B; their immunity protects them.
Why is an HCV RNA test done at 3 to 6 weeks?
Show answer
It finds a new hepatitis C infection much earlier than antibody testing.
How long does a course of HIV PEP last?
Show answer
28 days.
What precautions should a worker take while follow-up is under way?
Show answer
Use condoms, do not donate blood or tissue, discuss breastfeeding, avoid sharing razors or toothbrushes, and report illness.
How soon must a sharps injury be entered in the sharps injury log?
Show answer
Within 7 calendar days.
What did Northbridge learn from reviewing its sharps claims together?
Show answer
Three patterns: IV starts on restless patients, late activation of one blood collection set, and sharps in the laundry, each with a specific fix.
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.