
HSE-109 · Lesson 9 of 12 · 24 min
Accommodation, disability management and return to work
Even in workplaces with strong prevention, some workers will experience mental health conditions that affect their work, whether those conditions are caused by work, by life outside work or by a combination. How the workplace responds makes a big difference to recovery. Workers who are supported to stay at work with adjustments, or to return safely after an absence, generally recover better, keep their skills and income, and are less likely to move onto long-term disability. Poorly managed absences, by contrast, often become longer, more costly and more distressing for everyone involved. This lesson covers accommodation, staying at work, absence management and return to work for mental health conditions.
Why staying connected matters
Research on work disability consistently finds that the longer a person is off work, the less likely they are to return. For many mental health conditions, appropriate work can be part of recovery: it provides structure, purpose, social contact and income. That does not mean people should be pushed back too early, or that every condition allows work. It means the goal should be to keep people connected to work in a way that supports their health, and to plan return to work from the beginning of an absence, not at the end.
The US Department of Labor's Office of Disability Employment Policy promotes stay-at-work and return-to-work approaches, and its Job Accommodation Network (JAN) offers free, confidential guidance on accommodations, including for mental health conditions.
The duty to accommodate
Under the ADA, employers with 15 or more employees must provide reasonable accommodation to qualified individuals with disabilities, including mental health conditions, unless doing so would cause undue hardship, meaning significant difficulty or expense in light of the employer's size and resources. Usually the employee or someone on their behalf makes a request, which does not have to use the word accommodation; a statement that they need a change at work because of a medical condition is enough. The employer and employee then engage in an interactive process to identify the limitations and possible accommodations. The employer may ask for reasonable documentation of the disability and need when they are not obvious, but should not request complete medical records. The employer can choose among effective accommodations and is not required to lower production standards or eliminate essential functions.
Examples of accommodation
Accommodation for mental health conditions is often simple and low cost. The best accommodations are individualized, based on the person's specific functional limitations rather than their diagnosis, and developed with them.
| Functional limitation | Possible accommodations |
|---|---|
| Difficulty concentrating | Quiet workspace or noise-canceling headphones; fewer interruptions; written instructions; breaking tasks into steps |
| Fatigue or sleep problems, including from medication | Flexible start times; scheduled breaks; temporary removal from night shifts |
| Anxiety in certain situations | Advance notice of meetings and agendas; a support person at meetings; alternatives to presenting in large groups |
| Reduced stamina after an absence | Graduated return with reduced hours; temporary modified duties |
| Need to attend treatment | Flexible schedule or time off for appointments; ability to make up time |
| Difficulty with workload or prioritization | Regular check-ins; clear priorities; temporary reduction in workload; project management tools |
| Distress from particular interactions | Temporary reassignment away from a specific trigger; changes to reporting relationships where feasible |
Staying at work
Many people experiencing mental health problems can stay at work with temporary adjustments. When a worker discloses that they are struggling, or a supervisor notices signs (Lesson 7), the conversation can include what might help them continue working: a lighter workload for a few weeks, more flexible hours to attend appointments, a temporary change of tasks. Documented, time-limited stay-at-work plans, reviewed regularly, help everyone understand what has been agreed. Staying at work is not appropriate for everyone, and a health professional's advice should guide what is safe.
Managing an absence
When a worker needs time off, how the workplace behaves during the absence matters. Good practice includes:
- Early, compassionate contact, agreed with the worker: how often, by whom and by what means. Many people on mental health leave feel isolated and worry that they have been forgotten or will be judged.
- A designated contact person, often a disability management coordinator, HR advisor or trusted supervisor, rather than many different people calling.
- Clear information about pay, benefits, disability insurance, workers' compensation if applicable, and the return-to-work process.
- Respect for privacy: co-workers should be told only what the worker agrees to share, often just that they are away.
- Avoiding pressure: contact should be supportive, not a disguised push to return early or a review of work left undone.
- Keeping the job and connection open, for example by inviting the worker to social events if they wish, or sharing team news.
Planning the return to work
Return-to-work planning should start well before the return date. A good plan is developed collaboratively by the worker, the supervisor, HR or disability management and, where relevant, the union and the worker's health care provider. The health care provider typically supplies information about functional abilities and limitations and the expected duration of any restrictions, not the diagnosis. The plan sets out:
- The start date and a graduated schedule if needed, with hours and duties increasing over a set period.
- Any temporary modified duties or accommodations, and how long they will last.
- Who the worker will report to and who will check in, and how often.
- What co-workers will be told, as agreed with the worker.
- How progress will be reviewed and what happens if problems arise.
Worked problem
Building a graduated return-to-work schedule
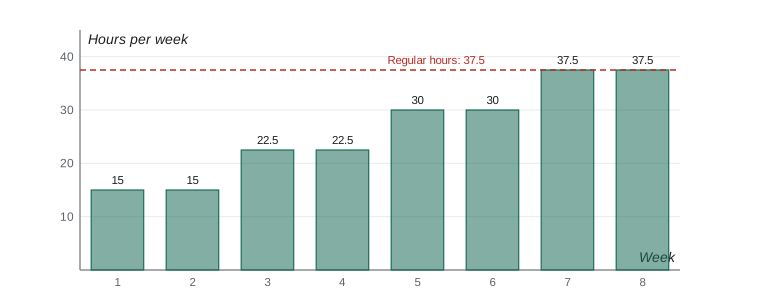
A worker returning after twelve weeks of leave for depression normally works 37.5 hours a week. Her health care provider says she can start at 40 percent of regular hours, increasing by 20 percentage points every two weeks, with no evening work for the first month. Calculate the weekly hours, the total hours worked over the eight-week plan, and the share of regular hours she will work over the whole plan.
Show solution
- Weeks 1 and 2 at 40 percent: \(0.40 \times 37.5 = 15\) hours a week.
- Weeks 3 and 4 at 60 percent: \(0.60 \times 37.5 = 22.5\) hours a week.
- Weeks 5 and 6 at 80 percent: \(0.80 \times 37.5 = 30\) hours a week.
- Weeks 7 and 8 at 100 percent: 37.5 hours a week.
- Total over eight weeks: \(2 \times (15 + 22.5 + 30 + 37.5) = 210\) hours.
- Regular hours over eight weeks: \(8 \times 37.5 = 300\) hours, so she works \(210 \div 300 = 70\) percent of regular hours over the plan.
- The schedule also needs agreed tasks for each stage, the no-evening restriction for weeks 1 to 4, and review points at weeks 2, 4 and 6.
Answer: Weekly hours of 15, 15, 22.5, 22.5, 30, 30, 37.5 and 37.5 total 210 hours, or 70 percent of regular hours over eight weeks, with review points built in.
The first weeks back
Returning to work after a mental health absence can be stressful. The worker may worry about what colleagues know or think, whether they can manage, and whether the problems that contributed to the absence have changed. Supervisors can help by welcoming the worker back warmly and naturally, meeting on the first day to go over the plan, giving clear priorities, checking in regularly without hovering, and responding quickly if difficulties arise. Co-workers can help by treating the person normally, including them, and respecting their privacy.
If work factors contributed to the absence, such as an excessive workload, conflict with a colleague or harassment, they need to be addressed before or as part of the return. Returning someone to the same unchanged conditions that made them ill sets them up to relapse. This is where accommodation and return to work connect with prevention: the lessons learned from individual cases should feed back into the organization's psychosocial risk assessment.
Supporting supervisors and co-workers
Accommodation and return to work also affect the people around the returning worker. Supervisors may be unsure what to say, worried about getting it wrong or stretched by covering for an absence. Co-workers may have picked up extra work and may not understand why a colleague now has different hours or duties. Organizations can help by giving supervisors guidance and access to HR or disability management advice, by planning coverage during absences so that the team is not simply overloaded, and by explaining, in general terms and without disclosing private information, that temporary adjustments are a normal part of supporting anyone returning from illness or injury. A team that sees colleagues being supported fairly is more likely to seek help early itself.
Workers' compensation and insurance
Where a mental health condition is accepted as work-related under a state workers' compensation system, the system's rules on benefits, medical care and return to work apply, and some states offer incentives for employers who provide transitional work. Where the condition is not work-related, short-term and long-term disability insurance plans typically manage the claim, sometimes alongside FMLA leave and state paid family and medical leave programs, which several states now offer. ADA duties to accommodate apply in every case, and leave itself can be a reasonable accommodation beyond FMLA in some circumstances.
When return to work does not go to plan
Not every return goes smoothly. Symptoms may return, a medication may cause side effects, or the worker may find a particular task or relationship harder than expected. Setbacks are common and do not mean the return has failed. The plan should say how setbacks will be handled: a quick conversation, a pause or slowing of the graduated schedule, a review of duties and, if needed, updated information from the health care provider. Responding calmly and flexibly keeps the worker connected and avoids turning a temporary setback into a long absence.
The business case for accommodation
Accommodation is often far cheaper than employers expect. Surveys of employers by the Job Accommodation Network have repeatedly found that about half of accommodations cost nothing, and most of the rest involve a modest one-time cost. Compared with the cost of a long absence, a disability claim or replacing a skilled worker, supporting someone to stay at work or return successfully is usually good value as well as the right thing to do.
Common mistakes
MistakeAsking for the worker's diagnosis.
InsteadAsk for functional abilities, limitations and expected duration from the health care provider.
MistakeLeaving the worker alone during leave so as not to bother them.
InsteadAgree on supportive, regular contact through a designated person.
MistakeWaiting until the end of an absence to plan the return.
InsteadStart return-to-work planning early and involve the worker.
MistakeReturning the worker to the same unchanged conditions that contributed to the absence.
InsteadAddress work factors such as workload, conflict or harassment as part of the plan.
MistakeTelling co-workers why the person was away.
InsteadShare only what the worker agrees to, often just that they are returning.
Summary and key terms
- Staying connected to work, with appropriate adjustments, generally supports recovery.
- US employers covered by the ADA must provide reasonable accommodation through an interactive process unless it causes undue hardship.
- Accommodations should be based on functional limitations, not diagnoses, and are often low cost.
- Good absence management involves early, supportive contact through a designated person and respect for privacy.
- Return-to-work plans are collaborative and often include graduated hours and temporary modified duties.
- Work factors that contributed to an absence must be addressed to prevent relapse.
- Workers' compensation, disability insurance and human rights or disability law all shape return to work.
- Accommodation
- A change to work, the workplace or how work is done that enables a person with a disability to work.
- Functional limitation
- A specific restriction in a person's ability to perform tasks.
- Undue hardship
- The point at which accommodation would cause excessive cost, difficulty or risk.
- Interactive process
- A collaborative dialogue to identify limitations and effective accommodations.
- Stay-at-work plan
- A time-limited plan of adjustments that allows a worker to keep working.
- Graduated return to work
- A return that increases hours or duties in stages.
- Modified duties
- Temporary changes to tasks that match a worker's current abilities.
- Disability management
- A coordinated approach to preventing disability and supporting return to work.
- Re-employment obligation
- A legal duty to offer an injured worker their job or suitable work.
- Relapse
- A return of symptoms after a period of improvement.
Practice problems
Work each problem on paper first, then reveal the answer to check.
Why should return-to-work planning start early?
Show answer
The longer a person is away, the harder return becomes, and early planning keeps them connected.
What information should an employer seek from a health care provider?
Show answer
Functional abilities, limitations and the expected duration of restrictions, not the diagnosis.
Give two accommodations for difficulty concentrating.
Show answer
For example, a quiet workspace and written instructions.
A worker normally works 40 hours. What are 50 and 75 percent of regular hours?
Show answer
20 and 30 hours a week.
Over a four-week plan of 20, 20, 30 and 40 hours, what share of regular 40-hour weeks is worked?
Show answer
110 ÷ 160 = 68.75 percent.
Who should be involved in developing a return-to-work plan?
Show answer
The worker, supervisor, HR or disability management, and where relevant the union and health care provider.
What should co-workers be told about a colleague's mental health leave?
Show answer
Only what the worker agrees to share.
Why must work factors be addressed before a return?
Show answer
Returning to unchanged harmful conditions risks relapse.
About what share of accommodations cost nothing, according to JAN surveys?
Show answer
About half.
Which free US service advises on accommodations?
Show answer
The Job Accommodation Network (JAN).
Lesson quiz · 5 questions
Score 60% or more to complete this lesson.
Create a free account to save your progress, take quizzes and earn a certificate.